# ADCs Move into First-Line Treatment: Which Differences Are Worth Paying For?
Start with how an ADC works, then ask how a scientific distinction becomes a usable treatment, a deliverable product and an asset worth partnering on.
**ADC-20261007-R1 → ADC-20261007-R1-LAYERED-HTML-R2-EVIDENCE-1.0**
Evidence as of 2026-10-07 (Asia/Taipei). Editorial organization / author attribution: Drugnews 藥時事. Complete English report; not published.
An antibody–drug conjugate (ADC) joins three components in one medicine: an antibody recognizes a cell-surface target; a linker connects the antibody and payload and influences stability and release; and a cytotoxic payload disrupts cancer-cell survival after reaching its site of action. This design allows delivery and cell killing to be improved separately, while failure at any step can limit the whole medicine.[R02](#R02)[R06](#R06)
The important industry shift is that some ADCs have moved from later treatment lines into first-line and early-stage cancer, while annual product sales can now be observed for a representative medicine. The next product faces changing standards of care, prior-treatment patterns and supply requirements. This report asks: **Which design improves a specific point of failure, what evidence supports its use, and what must a company deliver for that difference to merit payment?**[C01](#C01)[C02](#C02)[C03](#C03)[C06](#C06)[D35](#D35)
## Contents
- [01 How an ADC Works: Every Step Is a Design Question](#mechanism)
- [02 Sales Are Established; Earlier Use Changes Product Position](#position)
- [03 How Companies Turn Platforms into Deliverable Products](#competition)
- [04 Translate Engineering Labels into Testable Improvements](#technology)
- [05 Beyond “Next Generation”: How Mature Is the Evidence?](#maturity)
- [06 A Valuable Gap: What Comes after an ADC?](#sequence)
- [07 First-Line TNBC: Define the Patients before the Competition](#tnbc)
- [08 A Better Therapeutic Window Requires the Full Dosing Picture](#window)
- [09 A Mature Platform Still Faces Product-Specific Regulatory Tests](#regulatory)
- [10 Manufacturing: Qualified Batches and Flexible Commitments](#manufacturing)
- [11 What the Headline Deal Value Does Not Tell You](#transactions)
- [12 Taiwan’s Innovation: Different Technical Roles Need Different Evidence](#taiwan-innovation)
- [13 Delivery in Taiwan: Connecting Capabilities into Supply](#taiwan-delivery)
- [14 Which Events Could Change the Assessment over Twelve Months?](#events)
- [15 Connect the Value of a Difference to the Next Decision](#decision)
- [Appendix A Global Company and Collaboration Map](#global-map)
- [Appendix B Taiwan Capabilities and Evidence Map](#taiwan-map)
- [Appendix C Formulas, Source Scope and Update Method](#methods)
## 01 How an ADC Works: Every Step Is a Design Question
The antibody recognizes a cell-surface target, and the linker connects the antibody to a cytotoxic payload. The typical internalization route shown here proceeds through antigen binding, entry into an endosome, trafficking to a lysosome and design-dependent linker cleavage or antibody breakdown to release an active payload.[R02](#R02)[R06](#R06)
### P01|Which step should the next ADC improve?
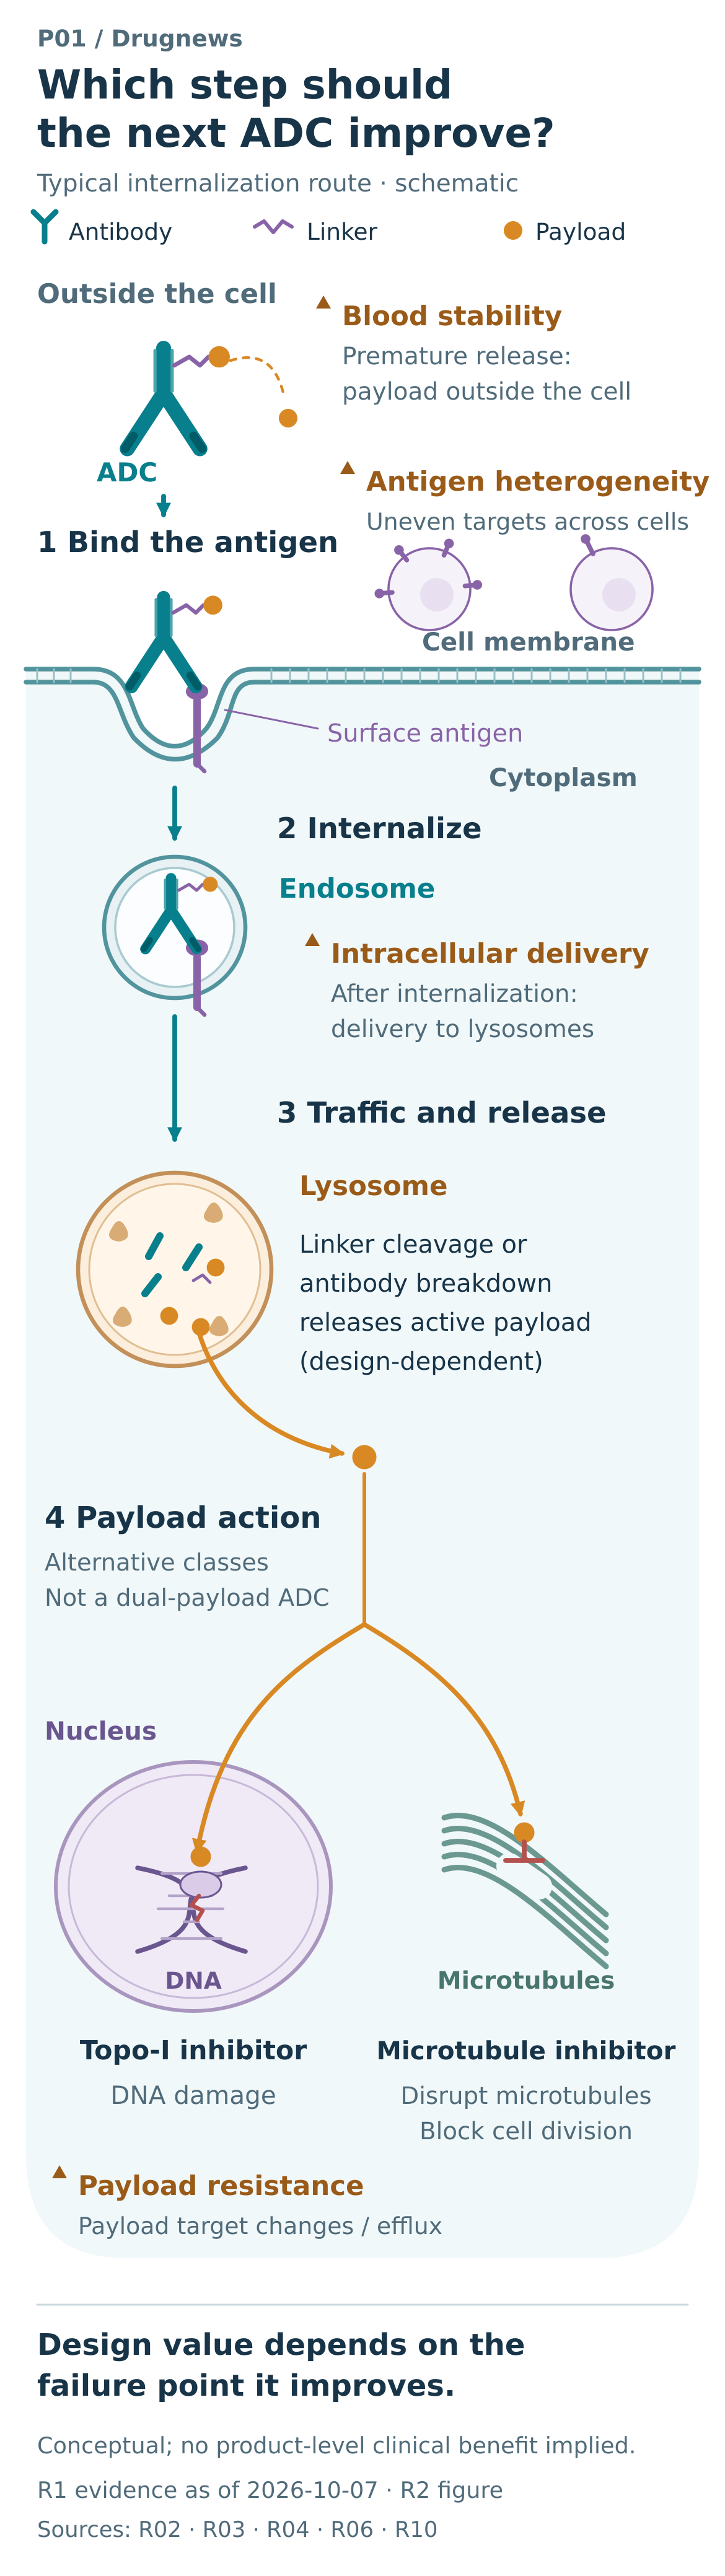
**How does an ADC deliver its payload to its site of action, and which failure point should a new design improve?**
A next-generation design is valuable for the failure point it improves.
Four testable points along the typical internalization pathway: stability in blood, antigen heterogeneity, intracellular delivery and payload resistance. The two payload-action branches represent alternative classes.
Research as of 2026-10-07; R10 published 2019-04-01 and checked 2026-10-07. Conceptual diagram; no numeric unit or currency. [R02](#R02)[R03](#R03)[R04](#R04)[R06](#R06)[R10](#R10)
[SVG](figures/P01_EN.svg) · [PNG](figures/P01_EN.png) · [P01_mechanism.json](data/P01_mechanism.json) · [Figure source index](figure_sources.json)
The site of action depends on the payload class: a Topo-I inhibitor affects DNA processing in the nucleus, while a microtubule inhibitor acts on cytoplasmic microtubules. These are alternative mechanisms. The conceptual diagram does not depict a dual-payload product or establish human benefit for a candidate.[R03](#R03)[R06](#R06)
The next design should therefore answer four questions: whether recognition is sufficient, whether payload is released prematurely, whether delivery continues after internalization, and whether the payload still works once it arrives. This turns technology labels into hypotheses that can be tested experimentally and then in humans.[R02](#R02)[R03](#R03)[R06](#R06)
## 02 Sales Are Established; Earlier Use Changes Product Position
ADC commercialization can already be observed directly in a representative product’s annual sales. Gilead’s 2025 Form 10-K reports that annual net product sales of Trodelvy (sacituzumab govitecan, abbreviated SG) rose from USD 1,063 million in 2023 to USD 1,315 million in 2024 and USD 1,397 million in 2025. Recalculated from these three disclosed values, year-on-year growth was 23.7% and 6.2%, respectively. This is one product’s total in Gilead’s consolidated accounts across the United States, Europe and the rest of the world, in nominal US dollars. It excludes any added collaboration payments or royalties and does not represent the global ADC market. [D35](#D35)
### P03|Trodelvy Sales Rose While Growth Slowed
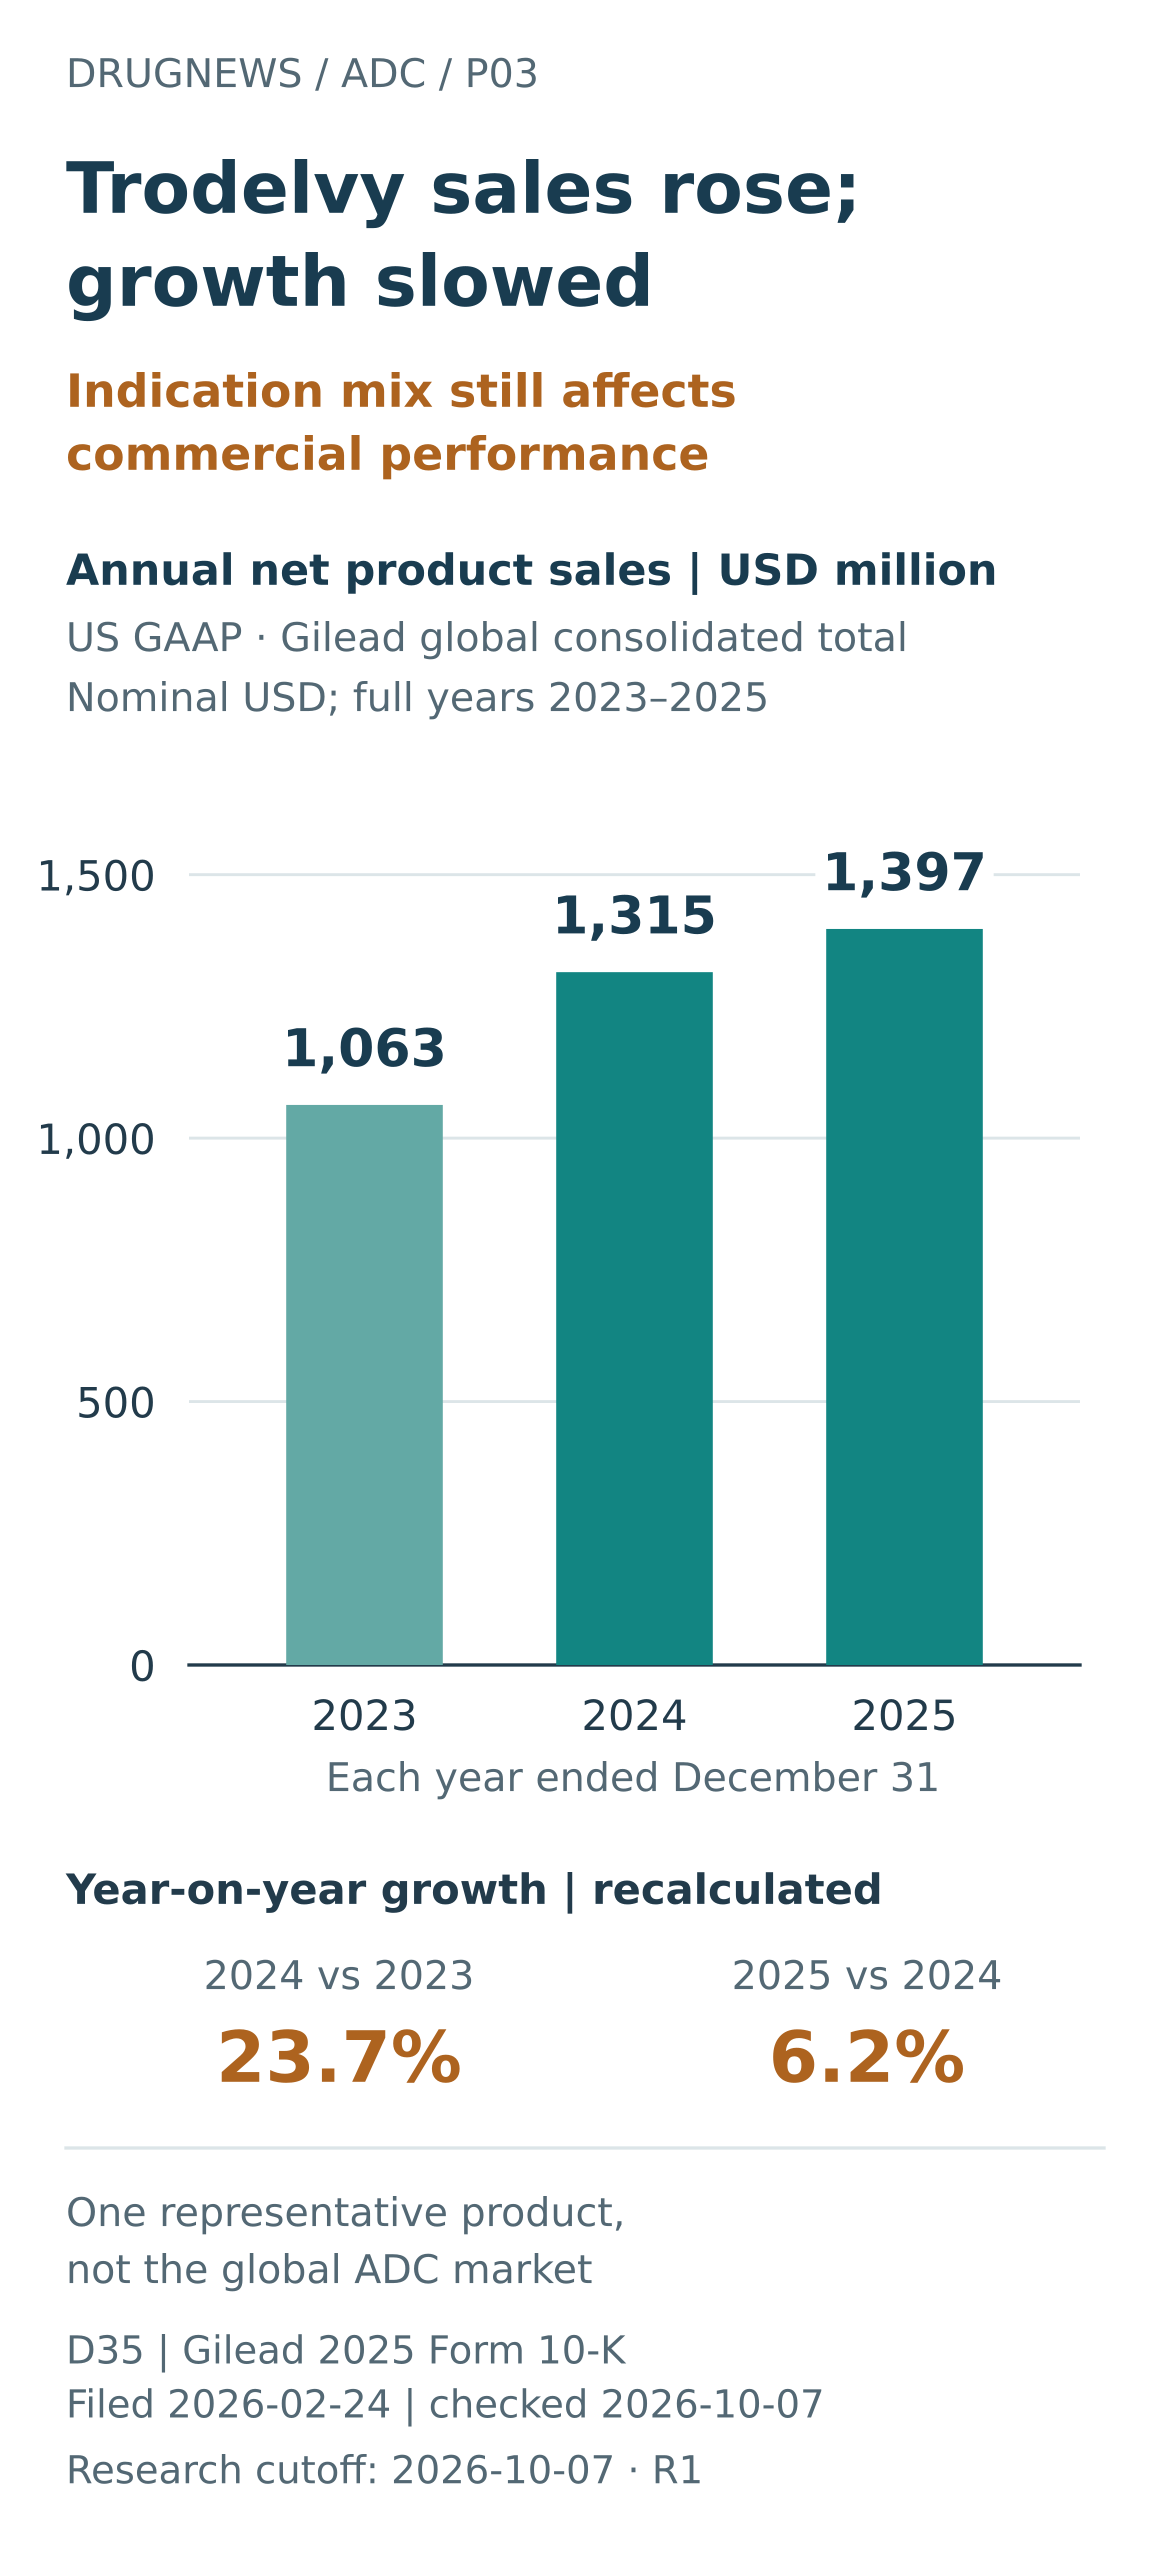
**Are actual sales of an established ADC still growing, and how has the pace changed?**
One product’s sales continue to rise, but growth must be read with its indication mix.
All three years come from the Trodelvy Total columns in the same table of Gilead’s 2025 Form 10-K. Original values, units and growth calculations are retained in adjacent text and data files. Bars start at zero; percentages are listed separately.
Full calendar/fiscal years end December 31. Gilead consolidated product totals across all reported regions; net product sales under US GAAP, in nominal USD. Filed 2026-02-24; checked 2026-10-07. [D35](#D35)
[SVG](figures/P03_EN.svg) · [PNG](figures/P03_EN.png) · [P03_sales.csv](data/P03_sales.csv) · [P03_sales.json](data/P03_sales.json) · [Figure source index](figure_sources.json)
Gilead attributed the 2025 increase primarily to demand in breast cancer treatment and stated that withdrawal of the bladder cancer indication partly offset that growth. This is management’s attribution; the filing does not quantify the contribution of each factor. For developers and buyers, the question is whether differentiation can preserve or expand an evidence-supported treatment position, and whether the same product’s other indications can sustain demand when an indication is lost. [D35](#D35)
Clinical differentiation and commercial delivery therefore need to be read together: randomized trials in earlier treatment lines can change the patient population a product addresses, while recognized sales also depend on actual product delivery and net price. This chart ends with the full 2025 calendar year; the first-line approvals in 2026 discussed later in the report cannot retrospectively explain 2025 sales. If a new design can establish an advantage that patients can continue to use in a defined population, while supporting reliable supply and clinical adoption, it may translate into product revenue.
### Earlier Treatment Changes the Patients the Next Medicine Faces
An ADC showing activity in heavily pretreated patients raises a different industry question from an ADC becoming an option in first-line or early-stage cancer. The former initially asks whether the molecule can treat the disease; the latter changes the patients enrolled in subsequent trials. As more patients receive ADCs, efficacy established in populations unexposed to these drugs needs to be reassessed.
### Table F01|Treatment Is Moving Earlier—and Changing the Sequencing Question
**Expanded approvals change patients’ prior treatment exposure and the questions the next trial must answer.**
| US approval date / setting | Specific change | Implication for subsequent development |
| --- | --- | --- |
| 2025-12-15
First-line HER2+ metastatic breast cancer | T-DXd (trastuzumab deruxtecan; Enhertu) + pertuzumab, supported by DB09.[C01](#C01) | If DXd has been used first-line, later-line research needs to describe prior ADC exposure. |
| 2026-05-15
HER2+ early-stage breast cancer | Neoadjuvant T-DXd → THP in stage II/III disease; a separate approval covers eligible patients with postoperative residual invasive disease.[C02](#C02) | The two approvals do not establish a validated sequence of neoadjuvant followed by adjuvant T-DXd. |
| 2026-05-22 / 06-24
Specific first-line TNBC settings | Dato-DXd (datopotamab deruxtecan; Datroway); SG alone or with pembrolizumab.[C03](#C03)[C06](#C06) | First distinguish immunotherapy suitability, PD-L1 criteria and prior treatment. |
| 2026-07-10
MIBC: candidates for cystectomy and eligible for cisplatin | Perioperative EV (enfortumab vedotin; Padcev) + pembrolizumab expanded to this population.[C08](#C08) | The full strategy before and after surgery, recurrence and survival must be assessed. |
Adjuvant T-DXd applies to residual invasive disease after neoadjuvant trastuzumab (with or without pertuzumab) and taxane therapy. THP = taxane + trastuzumab + pertuzumab; TNBC = triple-negative breast cancer; MIBC = muscle-invasive bladder cancer. A US approval does not imply approval or reimbursement in Taiwan on the same date.
[C01](#C01) [C02](#C02) [C03](#C03) [C06](#C06) [C08](#C08) · As of 2026-10-07; individual event dates are shown in the table.
### Moving earlier has three distinct meanings
First-line treatment of advanced disease emphasizes disease control and survival. Neoadjuvant treatment also asks whether more patients can achieve a pathological response at surgery, while adjuvant treatment asks whether recurrence can be reduced. The endpoints, treatment courses and acceptable risks differ. Pathological complete response (pCR) in DB11 and invasive disease-free survival (iDFS) in DB05 should each answer their own question.[C02](#C02)
In DB09, for example, median progression-free survival (PFS) was 40.7 months with T-DXd (Enhertu) + pertuzumab versus 26.9 months with THP; the hazard ratio (HR) was 0.56, with a 95% confidence interval (CI) of 0.44–0.71. This supports the first-line combination; overall survival (OS) was immature at the approval analysis. The trial’s third arm remained blinded in the published analysis, so these two groups do not isolate the additional contribution of pertuzumab to T-DXd.[C01](#C01)[C15](#C15)
As earlier treatment changes, positioning the next product starts with what patients have already received. This changes the population available for study, the standard comparator and the retreatment question. The value of a technical difference must be established from that new starting point.
## 03 How Companies Turn Platforms into Deliverable Products
The division of work in ADCs determines whether a scientific distinction can reach patients. Daiichi Sankyo connects different DXd candidates with different partners: its global alliances for Enhertu (T-DXd) and Datroway (Dato-DXd) began in March 2019 and July 2020, respectively; on October 19, 2023, it announced an alliance with Merck for HER3-DXd, I-DXd and R-DXd. The arrangements shown cover co-development and commercialization outside Japan; Daiichi Sankyo retains exclusive Japanese rights and is responsible for manufacturing and supply. This separates asset development, territorial rights and supply responsibilities. A buyer must assess whether the candidate’s clinical question is matched by a division of work that can be sustained through development. [R07](#R07)[D01](#D01)
### P04|Alliances, supply and ownership are different commitments
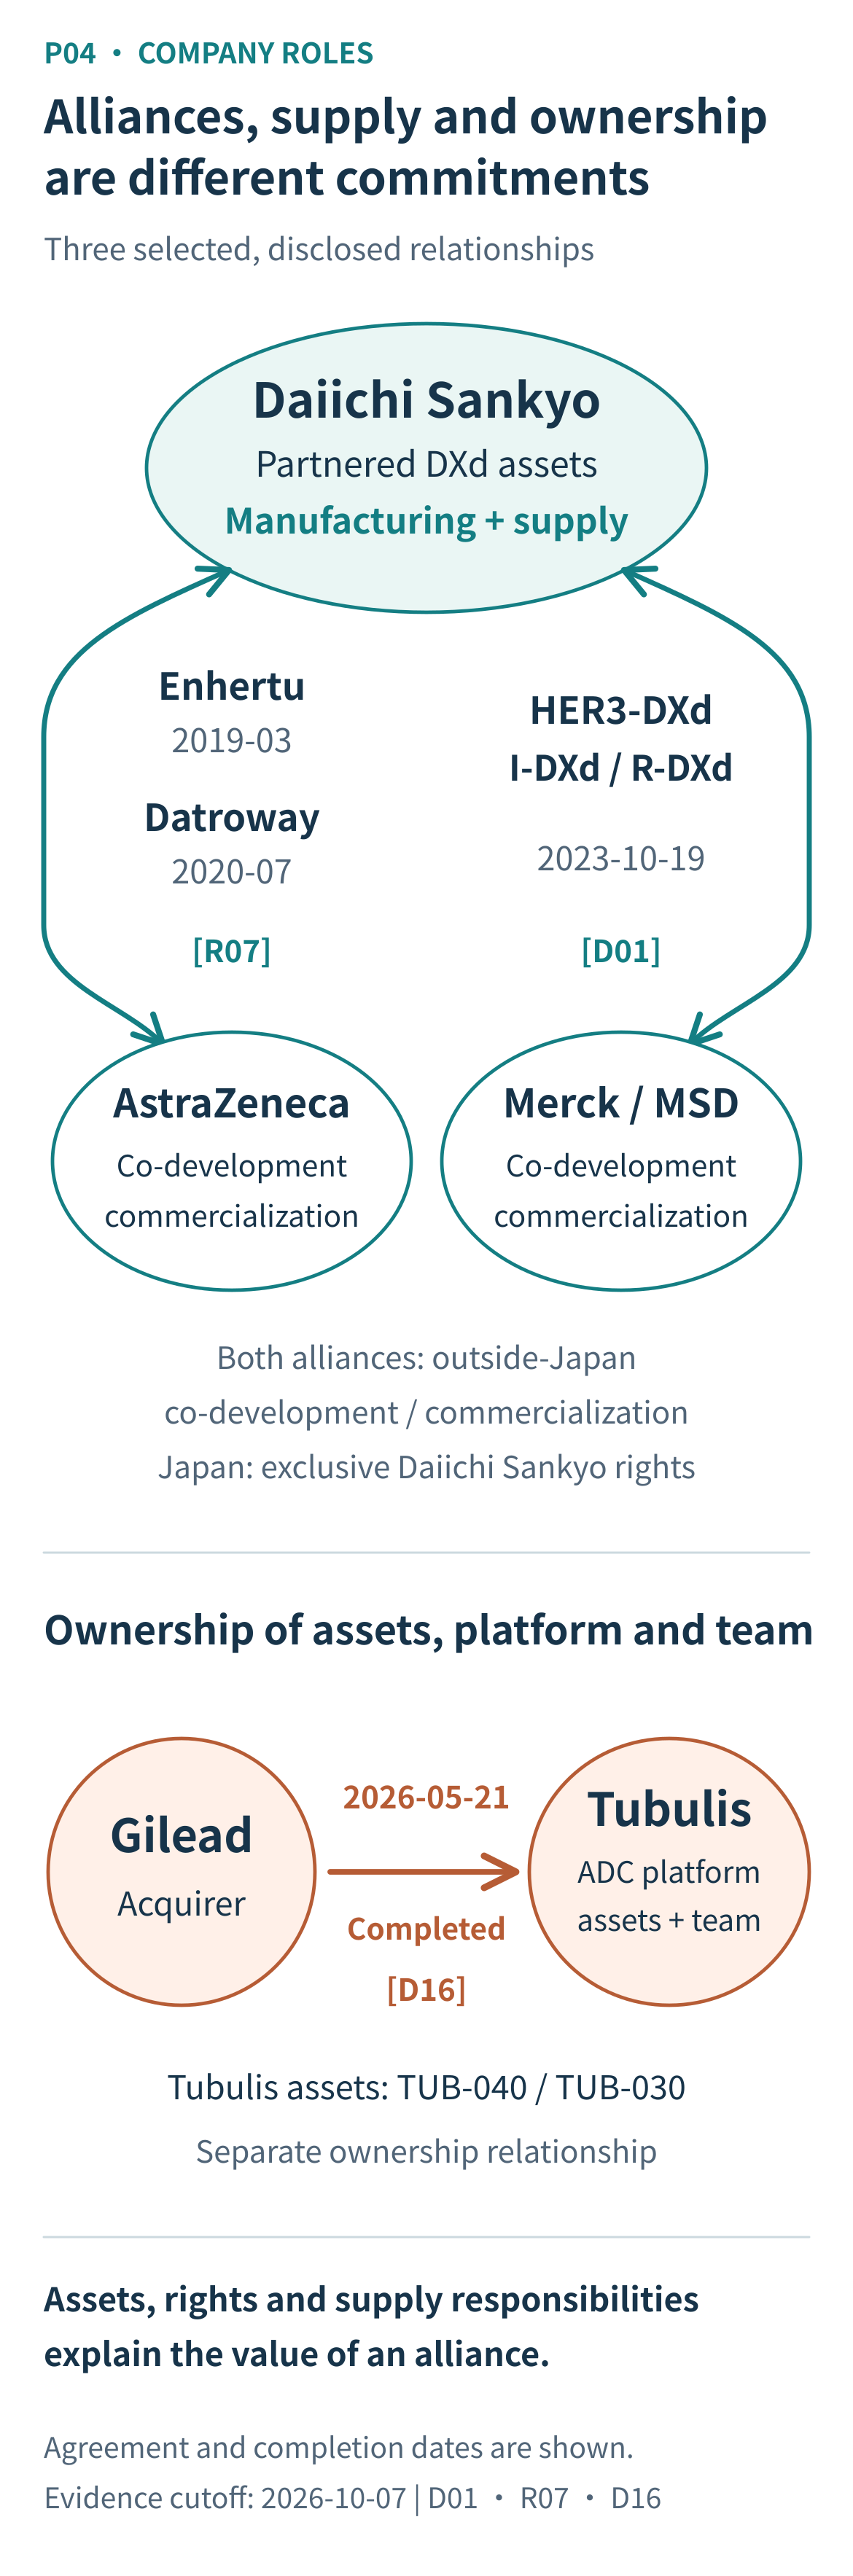
**When companies invest in ADCs, what do they obtain and who is responsible for moving each candidate forward?**
One DXd platform can connect with different global partners; assets, territorial rights and manufacturing responsibilities explain the value of each alliance.
Selected alliances already covered in R1: Daiichi Sankyo connects different DXd assets with AstraZeneca and Merck and is responsible for manufacturing and supply of the listed partnered assets. Gilead acquired Tubulis, including its assets, platform and team. Lines represent only the disclosed relationships shown. Original agreement dates appear in the figure; sources re-read on 2026-10-07. [D01](#D01)[R07](#R07)[D16](#D16)
Research as of / sources reread 2026-10-07. Alliances began 2019-03, 2020-07 and 2023-10-19; acquisition completed 2026-05-21. Arrows encode relationships, not monetary scale. [R07](#R07)[D01](#D01)[D16](#D16)
[SVG](figures/P04_EN.svg) · [PNG](figures/P04_EN.png) · [P04_roles.json](data/P04_roles.json) · [P04_edges.csv](data/P04_edges.csv) · [Figure source index](figure_sources.json)
Building ADC capability can also extend to owning an organization. Gilead completed its acquisition of Tubulis on May 21, 2026, bringing in TUB-040, TUB-030, its platform and its team; the team remains in Munich as an ADC innovation center. Acquiring a team and platform may support a continuing flow of candidates while bringing integration and development responsibilities into the group. The acquisition case therefore requires assessing both how far the lead asset can progress and whether the platform can deliver another developable candidate. The platform advantages described in the announcement still require product-level evidence. [D16](#D16)
### Table F09|Four Interfaces in Global Collaboration
**Drug companies can compete in monotherapy, collaborate on combinations, and use different transactions to strengthen development and supply capabilities.**
| Collaboration interface | Observed arrangement | Our assessment of the source of value |
| --- | --- | --- |
| Platform / candidate ↔ global development | Daiichi Sankyo with AZ and Merck; Duality with BioNTech.[D01](#D01)[D12](#D12)[D13](#D13)[R07](#R07) | Connect R&D assets to later-stage trials, commercial networks and capital; rights come with cost sharing. |
| Existing drugs ↔ new combinations | AZ / Daiichi Sankyo and Summit plan to evaluate Dato + ivonescimab.[R07](#R07) | If complementary effects are established, a new complete regimen could emerge; comparative trials remain necessary. |
| Collaboration → ownership of the organization | Gilead first collaborated with Tubulis, then completed its acquisition in 2026.[D14](#D14)[D15](#D15)[D16](#D16) | Expand the commitment after gaining familiarity, acquiring both assets and an R&D organization. |
| Conjugation technology ↔ process and supply | Lonza integrates Synaffix; WuXi XDC expands services in Singapore.[D22](#D22)[D23](#D23) | Transferable technology and execution across process stages can shorten the path from candidate to deliverable batch. |
Arrows indicate industry interfaces or changes in relationships; they do not imply direct contracts among every company shown. The final column presents the author’s inferences.
[D01](#D01) [D12](#D12) [D13](#D13) [D14](#D14) [D15](#D15) [D16](#D16) [D22](#D22) [D23](#D23) [R07](#R07) · Publicly disclosed relationships checked 2026-10-07
### The October 2026 Combination Collaboration Extends Competition to the Regimen
On 2026-10-02, AZ and Daiichi Sankyo announced a collaboration with Summit to evaluate Dato-DXd with the PD-1/VEGF bispecific antibody ivonescimab, with plans to begin in first-line TNBC. The parties will supply their respective medicines, share trial costs and retain the development and commercial rights to their own drugs. This is an announced collaboration plan, not evidence of combination efficacy. A planned Phase 3 start should not be described as a completed initiation.[R07](#R07)
We judge that such partnerships add another consideration for buyers: whether a molecule can form a usable regimen with an established or emerging immunotherapy. The questions include patient selection, overlapping toxicities, the contribution of each component, and benefit relative to the standard of care at the time. The USD 2 billion equity investment completed on 2026-10-05 should be recorded separately, so that the price paid for shares is not treated as an ADC license fee.[R08](#R08)
Duality’s exercise of its US cost- and profit/loss-sharing option for DB-1311 in May 2026 is another reminder that retaining more downstream value also entails greater funding and execution responsibilities. An industry map that shows only license arrows misses the sharing terms that can materially change the long-term economics of a collaboration.[D13](#D13)
## 04 Translate Engineering Labels into Testable Improvements
An ADC's performance reflects the combined effects of its antibody, linker, payload, conjugation distribution and dosing regimen. Improving one measure may alter other properties. A new platform should therefore be assessed by first specifying the constraint it aims to address and then deciding what to measure. Different approaches may complement one another, or move the bottleneck to the next step.[R02](#R02)
### Table F03|Which Point of Failure Does Each Design Address?
**A useful comparison links design changes to measurable problems, rather than assigning technology labels to generations.**
| Design choice | Main problem it seeks to improve | Measurements to examine |
| --- | --- | --- |
| Target / bispecific antibody | Uneven antigen distribution; insufficient binding or internalization | Target expression in enrolled patients; relationships among internalization and response; improvement relative to a comparator. |
| Intracellular delivery design | Inefficient delivery to lysosomes after internalization | Antibody–antigen dissociation, intracellular distribution and lysosomal accumulation; a 2019 preclinical anti-HER2 ADC example.[R10](#R10) |
| Conjugation design and DAR | Are product composition and stability controlled, and is exposure adequate? | DAR distribution, free payload, stability and human exposure. |
| Cleavable linker / permeable payload | Intratumoral release and coverage of neighboring low-expression cells | Bystander effects in tumor models, together with release in blood and tissue toxicity. |
| Switching payload mechanism | On-target resistance to the existing payload, efflux and related problems | Cross-resistance models, stratification by prior therapy and new limiting toxicities. |
| Dual payload / combination therapy | Complementary effects across cellular characteristics or disease pathways | Ratios, contribution of each component, sustainable dosing and cumulative toxicity. |
The questions and measurements form an analytical framework developed for this report; see F04 for evidence maturity. DAR = the average number of payload molecules attached per antibody; a distribution exists beyond the average.
[R02](#R02) [R04](#R04) [R06](#R06) [C10](#C10) [C11](#C11) [C12](#C12) [R10](#R10) · Literature: 2016–2026; checked 2026-10-07.
Delivery to lysosomes after internalization is also measurable. A 2019 preclinical anti-HER2 ADC study reduced antibody affinity for its antigen at acidic endosomal pH to promote dissociation; the study observed greater lysosomal ADC accumulation in cells. This is an antibody-binding and intracellular-delivery design example, not an acid-sensitive linker.[R10](#R10)
The bystander effect is a useful example. Membrane-permeable payloads can affect neighboring cells in cell and mouse models with mixed HER2 expression, offering a potential way to reach cells missed because of tumor heterogeneity. This provides a mechanistic basis, while also requiring developers to establish where payload release occurs and how much exposure normal tissues receive.[R04](#R04)
High DAR raises a similar issue. The assessment should focus on the physicochemical properties and in vivo behavior of the whole molecule: DAR distribution, free payload, storage stability and human exposure should be compared, rather than average DAR alone.
Patient selection can itself create a meaningful difference. To assess that difference, consider the timing of target testing, any retesting requirements and trial eligibility criteria together.
## 05 Beyond “Next Generation”: How Mature Is the Evidence?
Public evidence no longer supports treating all bispecific ADCs as concepts. Equating bispecificity with proven superiority over a single-target ADC also goes beyond the available comparisons. Evidence maturity becomes useful for research only when attached to a specific product, population and comparator.
### Table F04|Evidence Maturity Varies Across New Designs
**Bispecific ADCs have reached phase 3; new and dual payloads still require assessment of each product’s human development stage.**
| Example / design | Evidence available | Next critical gap |
| --- | --- | --- |
| Iza-bren
EGFR×HER3 / Topo-I | Original phase 3 publication in NPC in China; company-reported phase 3 TNBC/ESCC results.[C10](#C10)[C11](#C11) | Chemotherapy comparators do not isolate the incremental dual-target contribution; TNBC excluded prior TOPI ADCs.[C17](#C17) |
| HDP-101
BCMA / amanitin | 53 patients dosed in phase 1; the research poster lists an RP2D of 175 µg/kg; phase 2a expansion has begun.[C12](#C12) | Early multiple myeloma data; larger studies must validate dosing, efficacy and manageability. |
| MMAE + MMAF dual payload | Original research observed complementarity in mouse models of breast cancer heterogeneity/resistance.[R06](#R06) | Both are microtubule inhibitors; animal results do not yet establish benefit in humans. |
| DUPAC payload with a new mechanism | Genentech / Duality announced a preclinical collaboration and subsequent development handoff.[D18](#D18) | Overcoming resistance to existing payloads is a design claim awaiting human validation. |
| pH-dependent antigen dissociation / intracellular delivery | 2019 original anti-HER2 ADC study in cell and mouse models; engineered antibodies increased lysosomal ADC accumulation in cells.[R10](#R10) | Preclinical results in that study; they do not establish DCB platform claims or human benefit. |
Maturity is assessed for the specific product and sources obtained; another drug’s approval on the same platform is not a substitute. RP2D = recommended phase 2 dose.
[C10](#C10) [C11](#C11) [C12](#C12) [C17](#C17) [R06](#R06) [D18](#D18) [R10](#R10) · As of 2026-10-07; individual event dates are shown in the table.
In a phase 3 trial in China in recurrent/metastatic nasopharyngeal cancer, iza-bren was studied in patients previously treated with platinum-containing chemotherapy and PD-(L)1 therapy. The objective response rate (ORR) was 54.6% versus 27.0%, and grade ≥3 treatment-related adverse events occurred in 80% versus 62%. In 2026, the company also reported results from PANKU-Breast02 in China: among patients with TNBC who had received 1–2 prior lines of systemic therapy for advanced disease, OS was 15.9 versus 12.5 months, with an HR of 0.60 (95% CI 0.42–0.85). Both trials used chemotherapy comparators; the TNBC trial excluded prior TOPI ADC treatment.[C10](#C10)[C11](#C11)[C17](#C17)
HDP-101 uses a synthetic amanitin that inhibits RNA polymerase II, a mechanism distinct from Topo-I or microtubule-targeting payloads.[R09](#R09) Early human data make the development questions for this new mechanism concrete: how to select a dose, manage changes in platelet counts and liver tests, and establish durable efficacy. This multiple myeloma study has not answered whether the drug is effective in solid tumors after Topo-I ADC treatment.[C12](#C12)
In our assessment, the most persuasive case for an early platform combines a clear hypothesis with trials capable of disproving it. A transaction can demonstrate a buyer's willingness to share development risk; subsequent evidence is needed to turn that willingness into demonstrated clinical differentiation.
## 06 A Valuable Gap: What Comes after an ADC?
Topoisomerase I (TOP1) is the target of several ADC payloads, commonly grouped as Topo-I payloads. If a tumor develops resistance to this mechanism, switching the cell-surface antigen may not be sufficient. If failure instead occurs at the level of the antigen, internalization or payload delivery, a new antibody or conjugation design may help. The essential distinction is where treatment fails.[R02](#R02)[R03](#R03)
### Table F02|Three Evidence Gaps in ADC Sequencing
**Check who entered the trial before deciding whether a positive result answers the question of treatment after an ADC.**
| Question | Verified scope of the evidence | Additional evidence needed |
| --- | --- | --- |
| Can a payload from the same class follow? | TROPION-Breast02 and ASCENT-03/04 excluded prior Topo-I treatment / relevant ADCs.[C18](#C18)[C19](#C19)[C20](#C20) | Study patients whose earlier-line ADC failed, recording payload, interval and reason for progression. |
| Can a new dual-target ADC overcome failure? | PANKU-Breast02 with iza-bren excluded prior TOPI ADC treatment.[C17](#C17) | Test in a population with prior ADC exposure, using a meaningful comparator. |
| Can the drug be used before and after surgery? | DB05 excluded prior T-DXd, T-DM1 or other HER2 ADCs.[C21](#C21) | Explicitly design an adjuvant comparison after neoadjuvant T-DXd and track recurrence and toxicity. |
Registry updates: PANKU-Breast02, 2026-07-23; TROPION-Breast02, 2026-05-15; ASCENT-03, 2026-04-06; ASCENT-04, 2025-09-18; DB05, 2026-05-15.
[C17](#C17) [C18](#C18) [C19](#C19) [C20](#C20) [C21](#C21) · As of 2026-10-07; individual event dates are shown in the table.
Early-stage breast cancer requires the same precision. pCR was 67.3% versus 56.3% in DB11, and three-year iDFS was 92.4% versus 83.7% in DB05. The former compares neoadjuvant sequences; the latter directly compares postoperative T-DXd with T-DM1. Both findings have value, but the eligibility criteria in DB05 limit the conclusions that can be drawn by joining them together.[C02](#C02)[C21](#C21)
### TOP1 mutations offer a clue that still needs prospective validation
Abelman and colleagues detected TOP1 mutations in 4 of 31 selected patients with metastatic breast cancer who had plasma genomic testing after ADC treatment. A separate cohort of 420 patients who had not received ADCs included 3 such cases. The proportions were 12.9% and 0.7%, respectively, but the cohorts differed in their sources and selection. Functional experiments supported the possibility that some mutations confer cross-resistance to SN38 and DXd payloads.[R03](#R03)
This study provides a testable biological hypothesis: changing the target may still leave the same payload-related obstacle. It is not yet sufficient to make TOP1 variants a validated clinical exclusion rule. A more useful next step for developers is to collect pretreatment and post-treatment samples prospectively and include prior drugs, time to treatment failure and payload class in the analysis.
The post-ADC population is also heterogeneous. Patients who stopped because of toxicity, those whose disease progressed rapidly and those who progressed after prolonged control may have different needs from the next ADC. A trial that combines them into a single “prior ADC” category may still obscure the differences that matter.
## 07 First-Line TNBC: Define the Patients before the Competition
Triple-negative breast cancer (TNBC) provides a clear view of competition: suitability for PD-1/PD-L1 therapy, and whether PD-L1 meets a specified threshold, change the relevant treatment options. Defining those patient conditions first makes it possible to understand the use case supported by each randomized trial.[C03](#C03)[C06](#C06)
### P02|Three Within-Trial Comparisons Answer Separate First-Line Questions
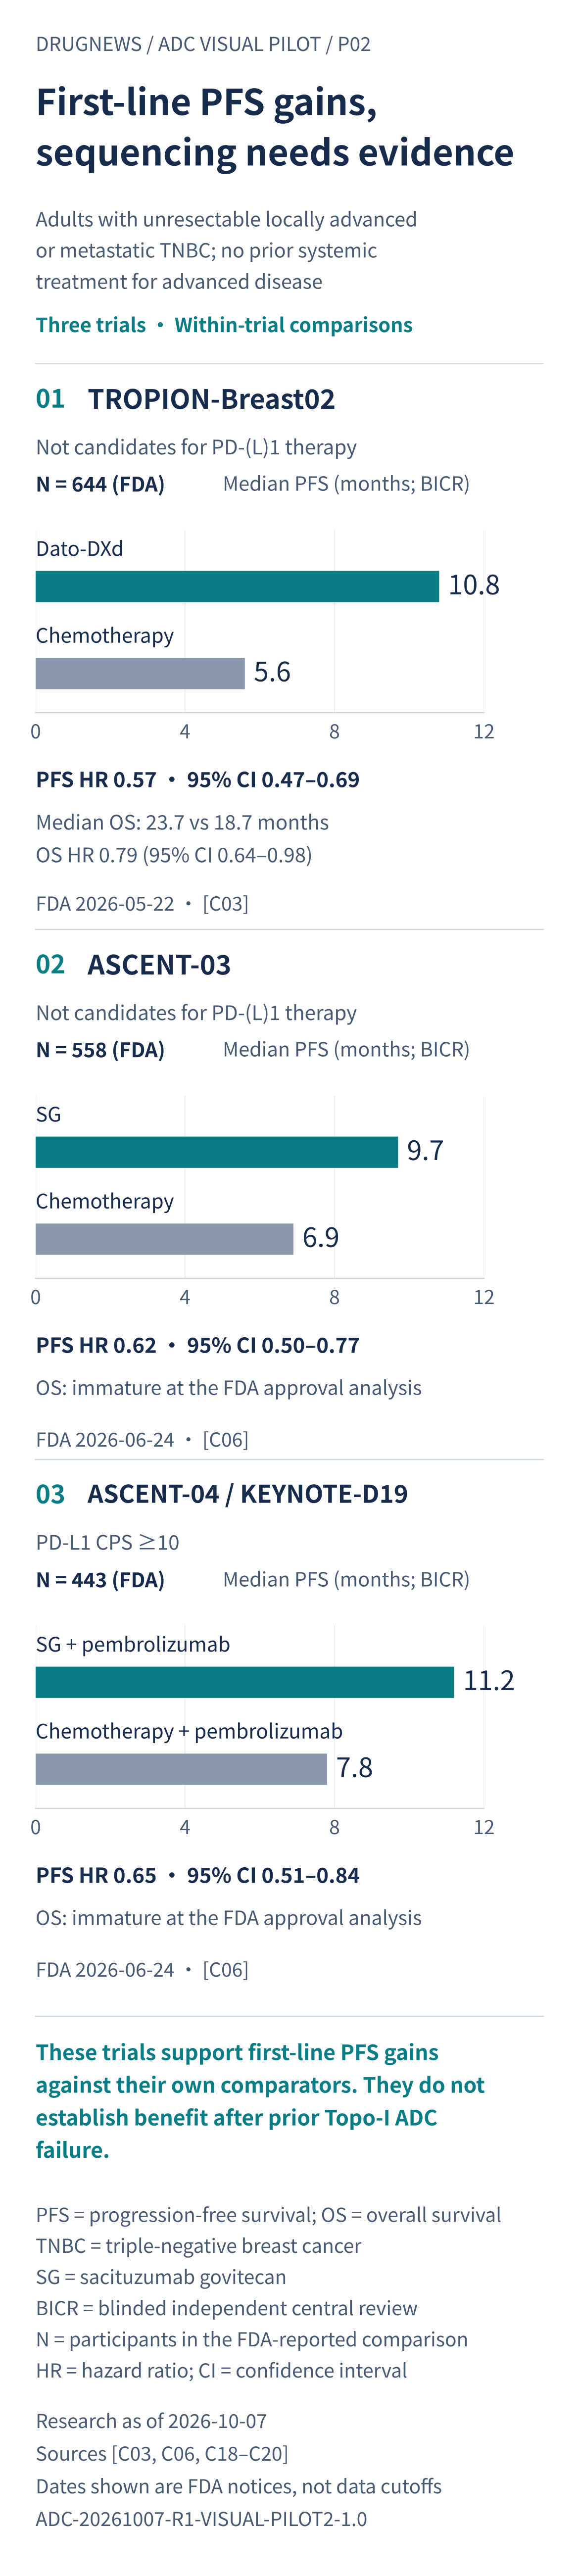
**For each trial’s patient population, what effect does the ADC show against that trial’s comparator?**
The trials support first-line efficacy in their respective populations; they do not establish efficacy after ADC failure.
Three separate panels compare median PFS only within each trial, in months; HR and 95% CI are listed separately. N, population conditions, comparators and FDA announcement dates are retained from the original data. An FDA announcement date is not a trial data cutoff.
Research as of 2026-10-07; FDA announcements 2026-05-22 / 2026-06-24. Trial data cutoffs are unknown. HR is dimensionless, PFS/OS are in months, N counts people; no currency. [C03](#C03)[C06](#C06)[C18](#C18)[C19](#C19)[C20](#C20)
[SVG](figures/P02_EN.svg) · [PNG](figures/P02_EN.png) · [P02_clinical.csv](data/P02_clinical.csv) · [P02_clinical.json](data/P02_clinical.json) · [Figure source index](figure_sources.json)
### Read the Four Statistical Labels First
PFS (progression-free survival) measures time before disease progression or death; its median is expressed in months. HR (hazard ratio) compares relative event rates during follow-up and has no unit of months; the 95% CI is the confidence interval around the HR estimate. N is the number of people in the stated analysis or trial and must be read with its population and source. Each panel’s bars show median PFS only. HR and CI are listed separately, not used as error bars on the medians.[C03](#C03)[C06](#C06)
### TROPION-Breast02 | Not Candidates for PD-(L)1 Therapy
The FDA notice lists N = 644. R1 also retains arm counts of 323 for Dato-DXd and 321 for chemotherapy. The trial compared Dato-DXd with investigator’s choice chemotherapy in adults with unresectable locally advanced or metastatic TNBC, no prior systemic treatment for advanced disease, and who were not candidates for PD-1/PD-L1 therapy.[C03](#C03)[C18](#C18)
Median PFS assessed by BICR (blinded independent central review) was **10.8 versus 5.6 months**; HR **0.57 (95% CI 0.47–0.69)**. Median OS (overall survival) was **23.7 versus 18.7 months**; OS HR **0.79 (95% CI 0.64–0.98)**. The FDA announcement date is **2026-05-22**, not a trial data cutoff.[C03](#C03)
### ASCENT-03 | Not Candidates for PD-(L)1 Therapy
The FDA notice lists N = 558. The population was likewise adults with unresectable locally advanced or metastatic TNBC, no prior systemic treatment for advanced disease, and who were not candidates for PD-1/PD-L1 therapy. SG was compared with nab-paclitaxel, paclitaxel, or gemcitabine + carboplatin.[C06](#C06)[C19](#C19)
BICR-assessed median PFS was **9.7 versus 6.9 months**; HR **0.62 (95% CI 0.50–0.77)**. OS was immature at the FDA approval analysis; the announcement date is **2026-06-24**. The registry separately lists 623 people as ACTUAL enrollment. This report has not obtained a verifiable explanation of the relationship between the FDA’s 558 and the registry’s 623; the figures are not interchangeable.[C06](#C06)[C19](#C19)
### ASCENT-04 / KEYNOTE-D19 | PD-L1 CPS ≥10
The FDA notice lists N = 443. Participants were adults with PD-L1 CPS ≥10, unresectable locally advanced or metastatic TNBC, and no prior systemic treatment for advanced disease. SG + pembrolizumab was compared with chemotherapy + pembrolizumab; both arms included immunotherapy.[C06](#C06)[C20](#C20)
BICR-assessed median PFS was **11.2 versus 7.8 months**; HR **0.65 (95% CI 0.51–0.84)**. OS was immature at the FDA approval analysis; the announcement date is **2026-06-24**.[C06](#C06)
Each panel supports first-line efficacy against that trial’s own comparator in its stated population. The results do not answer efficacy after a previous ADC has failed. This report has not obtained and verified the data cutoff for each of the three trials, so those fields remain unknown; FDA announcement and registry-update dates are separate and do not replace a data cutoff. All 25 original values remain in the unchanged source files. The relationship between FDA 558 and registry 623 remains unknown.[C18](#C18)[C19](#C19)[C20](#C20)
### Table F05|First-Line TNBC: Keep Each Trial’s Comparator in View
**These three trials support different treatment settings; none directly compares Dato-DXd with SG.**
| Trial / population | Comparison and N | Within-trial PFS | OS status |
| --- | --- | --- | --- |
| TROPION-Breast02
Not candidates for PD-(L)1 therapy | Dato-DXd vs chemotherapy
N = 644 | 10.8 vs 5.6 months
HR 0.57
95% CI 0.47–0.69 | 23.7 vs 18.7 months
HR 0.79
95% CI 0.64–0.98 |
| ASCENT-03
Not candidates for PD-(L)1 therapy | SG vs chemotherapy
N = 558 | 9.7 vs 6.9 months
HR 0.62
95% CI 0.50–0.77 | Still immature in the
FDA approval analysis |
| ASCENT-04
PD-L1 CPS≥10 | SG + pembrolizumab
vs chemotherapy + pembrolizumab
N = 443 | 11.2 vs 7.8 months
HR 0.65
95% CI 0.51–0.84 | Still immature in the
FDA approval analysis |
Trial populations were adults with unresectable locally advanced/metastatic TNBC who had not received systemic therapy for that advanced-disease setting. Immunotherapy criteria and chemotherapy options differed across trials. FDA announcements: 2026-05-22 and 06-24. Values are experimental arm vs control arm; N = number randomized; PFS = progression-free survival; OS = overall survival; CPS = combined positive score.
[C03](#C03) [C06](#C06) [C18](#C18) [C19](#C19) [C20](#C20) · Respective FDA approval analyses; checked 2026-10-07.
### For companies, clinical differences must become practical reasons for use
The approval analysis for Dato-DXd showed both PFS and OS benefits; OS remained immature at approval in ASCENT-03/04. This makes the evidence profiles different, but does not establish that one product is better than another. A head-to-head randomized trial remains the strongest evidence for comparing the relative benefits of the two drugs. Cross-trial patient-level analyses can add indirect evidence, while retaining the limitations arising from population differences and residual confounding.
Routine care is another area of competition. Managing ocular adverse reactions, oral mucositis and ILD with Dato-DXd differs from managing neutropenia and diarrhea with SG. A hospital's ability to deliver supportive care consistently will affect actual use. Public trial data, however, are insufficient to assign the same care costs across different health systems.[C03](#C03)[C06](#C06)
## 08 A Better Therapeutic Window Requires the Full Dosing Picture
A claim of “lower toxicity” needs to specify the toxicity assessed, the follow-up period and how much treatment patients actually received. The antibody, payload-conjugated component and released payload of an ADC can have different pharmacokinetics. FDA clinical pharmacology guidance therefore recommends evaluating the relevant components separately and using exposure–response relationships and the dosing regimen to support dose selection.[R02](#R02)
### Table F06|Four Types of Evidence Behind a Better Therapeutic Window
**Sustained dosing as planned can help translate molecular design into a benefit that patients and hospitals can use.**
| Evidence to examine | Why it changes the assessment | Example in this report |
| --- | --- | --- |
| Exposure and dose selection | Exposure to ADC, total antibody and free payload may change in different directions. | FDA recommends separate analysis of relevant components and exposure–response relationships.[R02](#R02) |
| Organ-specific and severe toxicity | Similar overall grade ≥3 rates may conceal different fatal or difficult-to-manage risks. | Overall grade ≥3 AE rates were similar in DB09; ILD occurrence differed.[C15](#C15) |
| Dosing delivered and supportive care | Dose reductions, delays, discontinuations and prophylaxis change sustainable exposure. | HDP-101 uses a split first dose and prophylactic measures to manage early toxicity.[C12](#C12) |
| Disease endpoints and patient burden | Tumor shrinkage, delayed progression, survival and outpatient care burden answer different questions. | Read TNBC trials alongside OS maturity and known management requirements.[C03](#C03)[C06](#C06) |
This table is a framework for reading evidence, not a cross-trial safety ranking. AE = adverse event; ILD = interstitial lung disease/pneumonitis.
[R02](#R02) [C15](#C15) [C12](#C12) [C03](#C03) [C06](#C06) · FDA guidance: 2024-03; clinical evidence: 2025–2026 versions, as specified in the source index.
In DB09, grade ≥3 adverse events occurred in 63.5% versus 62.3%, which appears similar. Yet adjudicated drug-related ILD/pneumonitis occurred in 12.1% versus 1.0%, with two grade 5 events in the T-DXd + pertuzumab arm. A single overall percentage can conceal different kinds of risk.[C15](#C15)
HDP-101 illustrates another point: the dosing schedule itself is part of product development. Splitting the first dose and using prophylactic measures aim to manage early changes in platelet counts and liver tests. If these adjustments allow patients to maintain meaningful exposure, they may broaden usability; the phase 1 findings still require confirmation in further expansion.[C12](#C12)
For industry readers, the next actionable research question is how planned treatment connects with treatment actually delivered: how many patients reduce, delay or stop dosing; how much exposure accumulates before discontinuation; and whether responding patients face the same care burden. These data can test a platform's practical product value and identify where dosing and supportive care still need improvement.
## 09 A Mature Platform Still Faces Product-Specific Regulatory Tests
### I-DXd withdrawal: early activity does not guarantee accelerated approval
On 2026-09-25, Daiichi Sankyo and Merck announced the voluntary withdrawal of the US biologics license application for ifinatamab deruxtecan (I-DXd) in certain previously treated patients with extensive-stage small cell lung cancer. The companies stated that, following discussions with the FDA, the data, including IDeate-Lung01, did not meet the requirements for the accelerated approval pathway. Further phase 3 development continued.[C13](#C13)
The conclusion this event supports is that a signal of activity can still fall short of the evidence needed for a particular regulatory pathway. The public withdrawal statement did not provide sufficient detail to attribute the decision to ILD, nor did it state that product development had ended. Attributing the withdrawal directly to a particular toxicity would turn an unresolved question into an established conclusion.
### HER3-DXd: the same product has faced distinct types of obstacles
When patritumab deruxtecan (HER3-DXd) received a complete response letter (CRL) in June 2024, the companies attributed it to inspection findings at a third-party manufacturing facility and stated that the letter identified no efficacy or safety issues with the submitted data. This report reviewed the companies' public account of the CRL, not the FDA's unpublished full letter.[D04](#D04)
In May 2025, the BLA was withdrawn after OS in HERTHENA-Lung02 failed to reach statistical significance and after discussions with the FDA. The two events need to remain separate: resolving a manufacturing problem does not automatically meet subsequent clinical evidence requirements, and the later withdrawal does not retrospectively invalidate the 2024 account of the inspection findings.[D05](#D05)
### How do these cases change the assessment of a partnership?
When a large pharmaceutical company acquires access to a mature platform, it can gain accumulated engineering, clinical operations and manufacturing knowledge. That experience does not guarantee results for a new target, population or line of therapy. In our assessment, due diligence should examine three questions individually: does the product offer sustained benefit; can the current trials answer the regulatory questions; and can the commercial manufacturing process reliably deliver the same product?
For sellers, transparency about unfinished comparisons, data maturity and manufacturing dependencies makes partnership terms more concrete. If the buyer needs to redesign trials, re-establish an appropriate dose or repeat a process transfer, each requirement affects downstream resources, timelines and payment arrangements. Separating these risks allows the parties to discuss who is best placed to bear them.
## 10 Manufacturing: Qualified Batches and Flexible Commitments
CMC (chemistry, manufacturing and controls) determines whether a candidate can be reproduced, scaled up and supplied consistently. ADCs span protein and highly potent chemical processes. Buyers need to understand which quality attributes can change at each handoff, and how the product will be shown to remain fit for use after a change.[R02](#R02)
### Table F07|Four Handoffs Define Value in ADC Manufacturing
**Buyers need reproducible, qualified products and evidence supporting transfer; vessel size describes only one equipment parameter.**
| Handoff | Verifiable deliverables | Risk easily overlooked |
| --- | --- | --- |
| Antibody → conjugation | Antibody quality, target binding, available conjugation sites and input consistency | Changes in starting materials may affect downstream reactions and the final product. |
| Payload/linker → reaction | Purity, impurities, stability and handling of highly potent compounds | Small-molecule and protein-process conditions may not be compatible. |
| Conjugation → purification and release | DAR distribution, aggregation, free payload, potency and batch comparability | A high yield accompanied by unacceptable impurities cannot become a saleable batch. |
| Drug substance → drug product / site transfer | Stability during storage, transport and filling; analytical and process transfer | Expansion, a site change or reformulation may require new comparability work. |
A buyer review framework developed from FDA guidance and publicly described services. Product specifications and regulatory requirements vary by product. No internal customer manuals were obtained or used.
[R02](#R02) [D21](#D21) [D22](#D22) [T09](#T09) [T10](#T10) [T11](#T11) · Public information checked 2026-10-07
### Daiichi Sankyo’s lesson: supply plans also need to evolve with the evidence
On 2026-05-08, Daiichi Sankyo announced that it had initially reserved capacity against maximum demand without risk adjustment, including minimum purchase obligations and dedicated production lines. Revisions to trial results, eligible patient populations and launch timelines subsequently led it to adopt a risk-adjusted supply plan. The company reported a JPY 75.7 billion provision for compensation to CMOs, and JPY 19.3 billion in impairment of Odawara equipment and estimated contract termination compensation.[D06](#D06)
These are different accounting charges. They cannot all be described as cash already paid, nor do they establish a technical failure to manufacture at scale. The company also stated that the difference between medium- to long-term purchase obligations and the revised plan had not yet been provided for because of substantial uncertainty. The supply question therefore extends from the amount of capacity available to when commitments are made, how much is committed, and who bears changes in demand.[D06](#D06)
We judge that capacity arrangements that can expand in stages, support technology transfer and assign clear quality responsibilities could become a partnership advantage. Lonza’s expected 2028 expansion and AZ’s 2029 target for its Singapore facility concern future supply. WuXi XDC’s 2026 GMP release is an operating milestone announced by the company. The three have different availability dates and levels of supporting evidence.[D21](#D21)[D23](#D23)[D24](#D24)
## 11 What the Headline Deal Value Does Not Tell You
ADC transactions include research options, asset licenses, co-development, acquisitions and equity investments. Similar headline amounts may cover different numbers of assets, territories, success conditions and subsequent expenditures. Separating the transaction types is the first step in understanding how much risk the buyer has taken on.
### Table F08|Five Transaction Types, Five Different Commitments
**Identify the nature of the payment and the scope of rights before using a headline value to assess risk allocation.**
| Transaction / original date | Amount and payment status (USD million) | Rights acquired / obligations assumed |
| --- | --- | --- |
| Merck / Daiichi Sankyo
2023-10-19 | Original agreement: 4,000 upfront + 1,500 continuation payments + up to 16,500 sales milestones; maximum 22,000. SEC-disclosed gross payments: 5,500.[D01](#D01)[D02](#D02) | Three DXd ADCs; co-development and commercialization outside Japan; Daiichi Sankyo responsible for manufacturing. |
| Gilead / Tubulis option
2024-12-03 | 20 upfront + 30 on exercise + up to 415 milestones; specified fees and milestones total up to 465, with sales royalties additional. Subsequent option-exercise payment not verified.[D14](#D14) | One research ADC against an undisclosed target; collaborate first, then decide whether to assume development. |
| Gilead acquisition of Tubulis
Completed 2026-05-21 | Agreed closing payment of 3,150 + up to 1,850 milestones. SEC reports approximately 3,200 net of acquired cash, a different accounting basis.[D15](#D15)[D16](#D16)[D17](#D17) | The company and its pipeline; SEC states that TUB-040 represented substantially all of the fair value of the assets acquired. |
| Genentech / Duality
2026-08-28 | 45 upfront + over 1,000 contingent milestones; no precise maximum. Actual receipt not verified.[D18](#D18) | DUPAC ADC; Duality develops through Phase 1a, after which Genentech takes over. |
| AZ / Summit equity
Completed 2026-10-05 | 2,000 equity investment; recorded separately from the 2026-10-02 clinical collaboration.[R07](#R07)[R08](#R08) | Equity ownership and a separate combination-trial collaboration; parties retain rights to their own drugs. |
All amounts are USD million. Original agreement values, accounting amounts net of acquired cash, gross payments and equity investments are not added into an industry deal total. Merck’s upfront payment includes a 1,000 component that is partly refundable; the 5,500 excludes R&D cost sharing and potential refunds.
[D01](#D01) [D02](#D02) [D14](#D14) [D15](#D15) [D16](#D16) [D17](#D17) [D18](#D18) [R07](#R07) [R08](#R08) · Transaction dates shown in rows; payment updates from Q2 2026 SEC filings and the 2026-10-05 announcement
Merck / Daiichi Sankyo illustrates why research needs incremental updates. The original 2023 agreement had a maximum value of USD 22 billion. The 2026 SEC filing read for R1 disclosed gross payments totaling USD 5.5 billion: a USD 4 billion upfront payment and two continuation payments of USD 750 million each, alongside conditions including R&D cost sharing and possible refunds. The filing also disclosed a July 2026 amendment to the sharing of certain clinical costs. Repeating only the headline maximum misses how the funding and execution responsibilities actually assumed have changed.[D01](#D01)[D02](#D02)
The Genentech–Duality agreement places the development handoff after Phase 1a. For the buyer, a meaningful question is whether the novel-mechanism payload can produce sustainable exposure and activity in a clinical candidate. For the seller, the quality of early delivery and a data package that the next team can use will matter to subsequent development. The announced milestone amount of “over USD 1 billion” has no precise ceiling, so an exact upfront share cannot be calculated from it.[D18](#D18)
## 12 Taiwan’s Innovation: Different Technical Roles Need Different Evidence
A single column asking whether a Taiwanese company has an ADC does not classify its role usefully. R1 selected entities with named assets or specific delivery capabilities from public pipelines, registries, technology-transfer offerings, licenses and service information. The selective map below is retained and assessed against the evidence required by each role. Listing status, tickers and their sources are listed in Appendix B; securities status and technical capability are assessed separately.
### OBI Pharma and GlycoNex: Both Work with Glycans, at Different Points in the ADC
OBI Pharma's GlycOBI uses antibody glycan sites for conjugation, primarily addressing where the payload is attached and how consistent the product is. OBI-902 is a TROP2 ADC using this approach, with a registry record showing human development. OBI-992 uses a different conjugation design; the two should remain distinct products. If human PK, sustainable dosing and activity support the engineering rationale, improved consistency may translate into product differentiation.[T01](#T01)[T02](#T02)[T03](#T03)
OBI Pharma's previously announced TegMine license illustrates one possible collaboration interface: a partner supplies a glycan-targeting antibody, combined with OBI Pharma's conjugation and linker technologies. The verifiable company-issued public release is dated January 12, 2026. Detailed financial terms were not disclosed, and the release does not confirm cash received; it cannot establish a realized order amount.[T04](#T04)
GlycoNex's GNX1021 instead recognizes the tumor-associated bLeB/Y glycan antigen, addressing what the ADC recognizes. On 2026-08-03, the company announced that the first patient had been dosed in Japan in its Phase 1 trial, an important transition from models to humans. Safety, dose and activity are the next evidence to track. Clinical data from other molecules cannot replace human evidence for the GNX1021 ADC itself.[T05](#T05)
### DCB: A Technology Lead Awaiting Verification
R1 included the Development Center for Biotechnology’s LYSward technology-transfer page.[T14](#T14) The independent QA carried forward into this round received HTTP 403 when rereading that page and could not verify its pH-design, trafficking or platform-maturity claims. R2 therefore retains these as a lead awaiting verification and does not use them to support the mechanism figure or evidence-maturity conclusion. The 2019 anti-HER2 ADC study discussed above supports a separate, verifiable preclinical design example; it does not establish the DCB platform’s claims.[R10](#R10)
### Formosa Pharmaceuticals / EirGenix: Similarity Offers a Different Kind of Product Value
TSY-110 (EG12043), jointly developed by Formosa Pharmaceuticals and EirGenix, references T-DM1 / Kadcyla. On 2026-08-28, Formosa Pharmaceuticals announced the submission of a clinical trial application in Europe; submission does not establish authorization or patient dosing. The core work concerns analytical similarity, PK, safety and immunogenicity. The separate EGFR × ROR1 asset TSY-310 was represented by preclinical data in the May 2026 announcement and requires its own assessment.[T06](#T06)[T07](#T07)
DB05 has directly compared T-DXd with T-DM1, so commercial research on a biosimilar also needs to update the reference product's future treatment position. If treatment choices shift, today's originator market cannot simply be treated as the market available to a future biosimilar. Access may create value, but pricing, reimbursement, remaining indications and actual uptake require region-specific assessment.[C02](#C02)
## 13 Delivery in Taiwan: Connecting Capabilities into Supply
Publicly identifiable capabilities in Taiwan span antibodies and analytics, highly potent small molecules, linkers, conjugation, purification and formulation. For international customers, value depends both on the technology and on whether data and responsibilities can be transferred effectively across companies, sites and development stages.[T09](#T09)[T10](#T10)[T12](#T12)[T13](#T13)
### Table F10|Taiwan's Manufacturing Capabilities: What Can a Buyer Verify?
**Turning service lists into delivery evidence may help build sustained collaboration.**
| Public capability / entity | Evidence available | The next most persuasive evidence |
| --- | --- | --- |
| EirGenix × Formosa Laboratories | Publicly described integration of antibody, analytical, highly potent chemistry and conjugation services.[T09](#T09)[T10](#T10) | Named or verifiable transfers across stages, batch release and records of supply under regulatory requirements. |
| Formosa Laboratories facilities | The company lists 30–200 L conjugation reactors, TFF, chromatography and related equipment.[T11](#T11) | Product-specific batch yield, acceptance rate, cycle time and demand alignment are needed to estimate deliverable output. |
| Mycenax / collaboration network | VLK license for CDMO use; the company lists GMP conjugation at 50 L scale.[T12](#T12)[T13](#T13) | ADC-specific analytical, release, technology-transfer and clinical-supply evidence, kept separate from unconjugated-antibody cases. |
| Shared commercial conditions | Work across companies involves materials, methods, quality responsibilities and scheduling. | Staged capacity reservations, changes in demand and technology-transfer responsibilities: criteria proposed by the author for assessing partnerships. |
Company-disclosed facility and service capabilities; product-specific batch and commercialization evidence require separate verification.
[T09](#T09) [T10](#T10) [T11](#T11) [T12](#T12) [T13](#T13) [D06](#D06) [R02](#R02) · Public service pages checked 2026-10-07; VLK license dated 2025-10-31
Public materials from EirGenix and Formosa Laboratories describe integration of the antibody and chemistry / conjugation components. Mycenax extends its services through a VLK technology license and a collaboration network. Published service and equipment information can define the scope of capability a company offers. The ability to supply a particular medicine over time still requires supporting batch and quality data.[T09](#T09)[T10](#T10)[T11](#T11)[T12](#T12)[T13](#T13)
Equipment volume and manufacturing scale are particularly easy to overinterpret. Protein concentration, reaction conditions, purification recovery and release specifications all affect qualified output. This report therefore preserves the distinction between Formosa Laboratories' 30–200 L reactor volumes and the 50 L GMP conjugation scale listed on Mycenax's service page. Neither figure is used to estimate qualified finished-product quantities, annual sales volume or revenue.[T11](#T11)[T13](#T13)
We judge that Taiwanese companies seeking greater visibility with potential partners would benefit most from publicly verifiable delivery cases: which stage of technology transfer has been completed, how analytical methods carry forward, where clinical supply or batch-release experience has been gained, and what evidence is needed for the next expansion of a collaboration. These details help buyers understand a company's responsibilities across the chain and allow researchers to track whether its capabilities are advancing.
## 14 Which Events Could Change the Assessment over Twelve Months?
A long list of future events is not a measure of research depth. This report distinguishes company guidance, trial-registry estimates and conditional watch items. The first two have traceable timing references; the third identifies evidence to await. Each update should begin by asking which assessment of a patient population, product or delivery capability the new information actually changes.
### Table F11|The Next Twelve Months: Which Events Could Change the Assessment?
**An event matters because of the assessment it may change; registry completion dates and company guidance are not guaranteed release dates.**
| Timing / type | Event | Question it could change |
| --- | --- | --- |
| H2 2026
Company guidance | AVANZAR; TROPION-Lung15. Latest guidance located: 2026-07-27.[C16](#C16) | Whether Dato establishes benefit in lung cancer under the specified combination, prior-treatment and biomarker conditions. |
| 2026-11-11
Registry estimate | DB09 primary completion; last updated 2026-07-30.[C22](#C22) | Whether a third arm or more mature follow-up can clarify the contribution of the combination. |
| Q4 2026
Company, event-driven estimate | Primary analysis of BNT323 DYNASTY-Breast02.[D26](#D26) | Whether later-stage comparative data can support development and the filing pathway. |
| H1 2027
Company guidance | TROPION-Lung07/08; latest guidance located: 2026-07-27.[C16](#C16) | Whether specific combinations and patient selection are supported in first-line lung cancer. |
| H2 2027
Partly outside this window | TROPION-Breast03; registry estimates primary completion on 2027-09-20.[C16](#C16)[C24](#C24) | Whether a subsequent strategy can reduce events in TNBC with residual disease after neoadjuvant treatment. |
| Conditional watch throughout the year
No confirmed announcement date | OBI-902/992 data, GNX1021, and TSY-110 regulatory and trial progress.[T02](#T02)[T03](#T03)[T05](#T05)[T06](#T06) | Whether the Taiwan cases advance toward evidence of sustainable dosing in humans, similarity, or delivery. |
Watch window: 2026-10-08 to 2027-10-07. The latest guidance does not confirm that results remain unpublished; announcements must be checked at each update. I-DXd’s BLA was withdrawn, so the former 2026-10-10 PDUFA date has been removed from the event list.
[C16](#C16) [C22](#C22) [C24](#C24) [D26](#D26) [T02](#T02) [T03](#T03) [T05](#T05) [T06](#T06) · Guidance and registry dates shown in rows; checked 2026-10-07
Changes in timing are themselves informative. The latest AZ guidance located places Lung07/08 in H1 2027. Following the withdrawal of the I-DXd application in September, its former 2026-10-10 PDUFA date is no longer a valid upcoming review milestone. The latest Lung02 registry entry estimates primary completion in January 2028, which also falls outside this twelve-month watchlist.[C16](#C16)[C13](#C13)[C23](#C23)
The conditions for changing an assessment should be specified before each readout. If a positive trial still excludes patients previously treated with the same ADC class, it may change the view of frontline competition while leaving the sequencing gap unresolved. If the main advance is the start of dosing, the update should reflect development maturity while efficacy remains unknown. This allows a monthly report to answer “What changed this month?” rather than simply reorder the news.
## 15 Connect the Value of a Difference to the Next Decision
The investment a difference merits depends on the patient gap it could address and the work still required to deliver a product. Public evidence does not yet support a universal success rate or price for every approach. This report offers a sequence of decisions that can evolve with the evidence.
### Table F12|Three Scenarios That Could Change R&D and Partnership Priorities
**A scenario tool should identify the evidence needed, rather than mask unknowns with apparently precise scores.**
| Scenario assumption | Priority evidence questions | Potential partnership adjustment |
| --- | --- | --- |
| A Frontline Topo-I ADC use increases while sequencing data remain limited | Clearly defined prior-exposure cohorts; mechanism of action and time to failure; a meaningful comparator | Prioritize sequencing trials and approaches with new mechanisms; link contingent payments to verifiable milestones. |
| B Treatment and supportive care become more sustainable at similar efficacy | Comparative discontinuation, dose reduction, patient-reported outcomes and care burden on hospitals | If the evidence is consistent, positioning could extend to usability; reimbursement and costs still require market-specific validation. |
| C Indication expectations are reduced or launch timelines are revised | Updated treatable population, trial and regulatory timelines, and existing capacity obligations | Revise demand scenarios and staged capacity commitments; redefine technology-transfer and supply responsibilities. |
These are author-developed scenarios without assigned probabilities, not market-size or valuation forecasts. Topo-I denotes the topoisomerase I payload class.
[R02](#R02) [R03](#R03) [D06](#D06) [C17](#C17) [C18](#C18) [C19](#C19) [C20](#C20) · Scenario baseline: 2026-10-07
For an innovative asset, first establish the target patients, current failure mechanisms and comparative endpoints, then examine actual exposure and toxicity. For a biosimilar, define the similarity development pathway and the reference product’s future treatment position. For a service capability, establish the quality handoffs and the scope that can be delivered. Conflating these three starting points risks choosing the wrong evidence and transaction comparators.
### Further reading and enterprise research
This free report provides the complete argument, company maps and data for recalculation. The additional value of membership research should come from continuing updates, company tracking and scenario tools: which assumptions new evidence supports, which should be withdrawn, and which evidence to follow next. The [Drugnews in-depth research page](https://drugnews.com.tw/subscribe.html) describes the existing subscription content and subsequent research.[T21](#T21)
The additional value of an annual enterprise engagement is to extend the same research into tailored questions, competitive positioning and execution throughout the year—for example, mapping a company’s evidence gaps, developing its milestone narrative and establishing an update cadence. The [Drugnews enterprise collaboration page](https://drugnews.com.tw/services.html) provides an entry point to discuss an appropriate scope. Engagement terms and the actual services are confirmed through the existing process.[T22](#T22)
## Appendix A Global Company and Collaboration Map
### Table F13|Global Company Map: Selected by Competitive Role
**Understanding the roles an organization already holds helps explain what it needs to acquire, access through partnership, or build internally.**
| Entity | Substantive ADC position / relationship | Focus for tracking |
| --- | --- | --- |
| Daiichi Sankyo / AZ | DXd candidates, marketed products and co-development; AZ also pursues manufacturing investment.[D01](#D01)[D24](#D24)[R07](#R07) | Frontline and combination data; supply commitments. |
| Merck | Co-development of I-DXd, HER3-DXd and R-DXd; traceable payments and contract amendments.[D01](#D01)[D02](#D02)[D05](#D05) | Comparative evidence required for regulatory review. |
| Pfizer / Seagen | Pfizer completed its acquisition of all outstanding Seagen common stock in December 2023.[D07](#D07) | Extension of the existing portfolio into earlier treatment lines. |
| Astellas / Pfizer | Perioperative EV in MIBC: expanded US approval; positive CHMP opinion in Europe.[D27](#D27)[C08](#C08) | The overall perioperative treatment strategy. |
| AbbVie / ImmunoGen | Acquisition completed in February 2024; ELAHERE and the ADC pipeline became part of the group.[D10](#D10) | The marketed product entry point and subsequent pipeline. |
| Gilead / Tubulis | SG commercial portfolio; acquired Tubulis and assets including TUB-040 in May 2026.[C06](#C06)[D16](#D16)[D17](#D17) | Human data for new assets and their integration. |
| BioNTech / Duality | Co-development of BNT323 and BNT324; US profit/loss-sharing option exercised.[D12](#D12)[D13](#D13)[D26](#D26) | Later-stage data and actual funding commitments. |
| Roche / Genentech | Genentech signed a DUPAC collaboration involving a novel-mechanism payload.[D18](#D18) | De-risking evidence before the Phase 1a handoff. |
| BMS / SystImmune | Joint development of Iza-bren outside China; Biokin sponsors PANKU-Breast02 and PANKU-Esophagus01 in China.[C11](#C11) | Applicability of the patient populations and comparators. |
| Lonza / Synaffix | Integration of conjugation platforms, prototyping, analytics and manufacturing.[D21](#D21)[D22](#D22) | Capacity entering service and processes ready for transfer. |
| WuXi XDC | Company-announced GMP release at its Singapore site and further expansion.[D23](#D23) | Supply capabilities and product-specific validation. |
| Summit | Ivonescimab combination collaboration; separate equity investment from AZ.[R07](#R07)[R08](#R08) | Combination-trial initiation and design. |
Entries represent selected groups or partnerships. Row counts do not indicate the number of independent companies, overall market rankings or every scope of rights. Global securities identifiers are retained in the master data; this figure focuses on roles.
[D01](#D01) [D02](#D02) [D05](#D05) [D07](#D07) [D10](#D10) [D12](#D12) [D13](#D13) [D16](#D16) [D17](#D17) [D18](#D18) [D21](#D21) [D22](#D22) [D23](#D23) [D24](#D24) [D26](#D26) [D27](#D27) [C06](#C06) [C08](#C08) [C11](#C11) [R07](#R07) [R08](#R08) · Public relationships and organizational status checked 2026-10-07
Inclusion criteria: a direct connection to this report’s questions about frontline or sequential treatment, payloads and conjugation, representative transactions, or manufacturing delivery. The master data also retain the original transaction types and securities identifiers. Acquired companies are not treated as independently listed entities. The map does not enumerate every target, early-stage startup or regional license.
## Appendix B Taiwan Capabilities and Evidence Map
### Table F14|Taiwan's Capability Map: Seven Entities, Three Types of Need
**Read six corporate entities by role; DCB is retained separately as a source lead awaiting verification.**
| Entity / securities status at cutoff | Substantive link and public evidence maturity | Evidence still needed |
| --- | --- | --- |
| OBI Pharma
TPEx-listed 4174 [T18](#T18) | GlycOBI glycan-site conjugation; OBI-902 in human trials; TegMine license announced.[T01](#T01)[T03](#T03)[T04](#T04) | Human PK, sustainable dosing and meaningful activity; license amounts undisclosed. |
| GlycoNex
TPEx-listed 4168 [T19](#T19) | GNX1021 targets the bLeB/Y glycan antigen; company announced first patient dosed on 2026-08-03.[T05](#T05) | Human safety, dose and preliminary efficacy; requires data on the GNX1021 ADC itself. |
| Formosa Pharmaceuticals
TWSE-listed 6838 [T17](#T17) | TSY-110 / EG12043 is a biosimilar candidate referencing T-DM1; European CTA submitted. TSY-310 preclinical data were announced in May 2026.[T06](#T06)[T07](#T07) | Progress after CTA submission and evidence of similarity; the bispecific asset separately awaits human evidence. |
| EirGenix
TWSE-listed 6589 [T16](#T16) | Antibodies, analytics and manufacturing; co-development of TSY-110 and services linked with Formosa Laboratories.[T06](#T06)[T09](#T09) | Product similarity and delivery records across stages. |
| Formosa Laboratories
TWSE-listed 4746 [T15](#T15) | Highly potent chemistry, conjugation, purification and formulation; lists 30–200 L reactors.[T10](#T10)[T11](#T11) | Product-specific batch yields, release and technology transfer; vessel volume is not annual output. |
| Mycenax
TPEx-listed 4726 [T20](#T20) | Rights to use VLK linker technology for CDMO services; company lists GMP conjugation at 50 L scale.[T12](#T12)[T13](#T13) | ADC clinical-supply / batch evidence, kept separate from unconjugated-antibody cases. |
| Development Center for Biotechnology (DCB)
Research organization; no ticker | R1 included the LYSward technology-transfer page. External QA in this round received HTTP 403; technical claims and platform maturity await verification.[T14](#T14) | Obtain normally accessible direct public support before assessing the technology and candidates; R10 does not validate DCB. |
Securities-status sources are separate from capability sources. EirGenix transferred to the TWSE on 2025-07-21. The TWSE company-profile PDFs available for this check were generated on 2026-10-07. For company pages with no update date, only the access date is recorded; it is not treated as the date on which capability or capacity was updated.
[T01](#T01) [T03](#T03) [T04](#T04) [T05](#T05) [T06](#T06) [T07](#T07) [T09](#T09) [T10](#T10) [T11](#T11) [T12](#T12) [T13](#T13) [T14](#T14) [T15](#T15) [T16](#T16) [T17](#T17) [T18](#T18) [T19](#T19) [T20](#T20) · Checked 2026-10-07; dates for individual clinical and facility information are in the sources
This map should change as evidence changes. The threshold for adding a company is a verifiable, named ADC, trial, transaction, technology license or delivery capability. For companies already included, update their status and sources before deciding whether their role has changed. A collaboration announcement does not automatically turn a service provider into an innovative drug company with demonstrated clinical advantages.
## Appendix C Formulas, Source Scope and Update Method
Year-on-year growth is (current-year sales / prior-year sales − 1) × 100%. Trodelvy inputs are USD 1,063 million, USD 1,315 million and USD 1,397 million; the 2024 and 2025 results are 23.7% and 6.2%. These are recalculated from reported whole-million values and rounded to one decimal place. A preceding-year value for 2023 was not obtained in this increment, so no zero or estimate is inserted.[D35](#D35)
### Table F15|Reproducible Data: Retaining Both Formulas and Units
**Within-trial numerical differences can be recalculated; they do not establish individual benefit or rankings across trials.**
| Calculation | Original inputs and formula | Result / interpretation |
| --- | --- | --- |
| DB11 pCR difference | 67.3% − 56.3% [C02](#C02) | 11.0 percentage points; a difference in pathological response, not a cure rate. |
| DB05 3-year iDFS difference | 92.4% − 83.7% [C02](#C02) | 8.7 percentage points; an estimated difference at a specific time point. |
| DB09 median PFS difference | 40.7 months − 26.9 months [C01](#C01) | 13.8 months; the difference between two group medians. |
| TOP1 detection proportions | 4 ÷ 31; separately, 3 ÷ 420 [R03](#R03) | 12.9%; 0.7%. Differently selected cohorts; these cannot be converted into a causal risk ratio. |
| Merck / DS disclosed gross payments | 4,000 + 750 + 750 [D02](#D02) | USD 5,500 million; excludes shared R&D costs and potential refunds. |
| 2024 Tubulis option: nominal maximum | 20 + 30 + 415 [D14](#D14) | USD 465 million; includes conditional payments, excludes sales royalties, and is not treated as cash received. |
| Trodelvy annual sales growth | (1,315 / 1,063 − 1) × 100%; (1,397 / 1,315 − 1) × 100% [D35](#D35) | 2024: 23.7%; 2025: 6.2%. Original inputs are USD million; recalculated from reported whole-million values. |
The original R1 Excel file is retained separately. R2 CSV/JSON retain original inputs and added calculations. Percentage points, months, ratios and monetary values remain distinct; ratio results are stored as 0–1 decimals. Unknown amounts remain blank and original currencies are retained.
[C01](#C01) [C02](#C02) [R03](#R03) [D02](#D02) [D14](#D14) [D35](#D35) · Data versions follow the individual sources; recalculated 2026-10-07
### Reading the Evidence: What Was and Was Not Accessed
This report uses lawful public regulatory notices, trial registries, original research, company releases and formal financial filings. The source index records publication dates, data dates and the material actually obtained. Original excerpts, supported locations and remaining evidence gaps are available in the [source evidence index](source_evidence.json) and [complete gap list](coverage.md).
The public Stifel entry page provided only the introduction, author information and download form for its IRIS rare-disease report. The full report was not obtained, and the form was not submitted. This report uses its own questions and maps of roles and evidence. It does not translate or reproduce Stifel's report, and the landing page is not used to support ADC facts.[R01](#R01)
### One Master Dataset for Daily Updates and Monthly Analysis
Updates use the same research master. Each record retains its ID, units, population, comparator, data date, evidence stage and sources. Fields change only when new evidence warrants an update; monthly coverage explains “previous judgment → new evidence → changed conclusion” rather than rewriting the same report.
Common abbreviations: T-DXd = trastuzumab deruxtecan (Enhertu); Dato-DXd = datopotamab deruxtecan (Datroway); SG = sacituzumab govitecan (Trodelvy); EV = enfortumab vedotin (Padcev). HR denotes hazard ratio, reflecting the relative event rate during follow-up; 95% CI denotes the 95% confidence interval. An HR is not an absolute risk difference at a particular time point.[C01](#C01)[C03](#C03)[C06](#C06)[C08](#C08)
Research parent: ADC-20261007-R1; source-supplement version: ADC-20261007-R1-LAYERED-HTML-R2-EVIDENCE-1.0. Research evidence is as of 2026-10-07 (Asia/Taipei). Corrections retain the original location, before-and-after wording in both languages and the associated sources; see [changes and versions](changes.md).
## Source Index
Publication, data and access dates are separate; an access date does not replace an unspecified date. Each source records the material actually obtained, supported locations and specific unknowns, with links to available original evidence. [Source evidence](source_evidence.json) · [Gap list](coverage.md)
### R01|[Stifel IRIS - Mapping Rare Disease in 2026: public introduction page](https://preferences.stifel.com/stifel-iris-rare-disease)
Publication / data / access: 2026-01-29 / 2026-01-29 / 2026-10-07
Public introduction and access scope; full text not obtained and not used for ADC facts.
Introduction, author information and download form read; the white paper's full text was not obtained, and the form was not submitted.
R1 access scope retained; not reread in this round
### R02|[FDA — Clinical Pharmacology Considerations for Antibody-Drug Conjugates Guidance for Industry](https://www.fda.gov/media/155997/download)
Publication / data / access: 2024-03 / 2024-03 / 2026-10-07
ADC and payload exposure, dose exploration, and comparability after manufacturing changes.
Full 13-page public guidance; the current FDA guidance entry page was also checked.
R1 access scope retained; not reread in this round
### R03|[Abelman et al. — TOP1 Mutations and Cross-Resistance to Antibody–Drug Conjugates in Patients with Metastatic Breast Cancer](https://pmc.ncbi.nlm.nih.gov/articles/PMC12079096/)
Publication / data / access: 2025-01-02 / Testing data: 2020-09 to 2024-01; journal issue: 2025-05-15 / 2026-10-07
The existing abstract-supported 4/31, 3/420 and cross-resistance scope are retained. The unverified individual baseline-case detail has been removed.
Only the baseline detail in Table 1 or the case passage was reopened. The original page returned reCAPTCHA and reading stopped; that passage was not obtained. The existing abstract-supported scope was not rechecked. Locator: Existing abstract scope carried forward; Table 1 / case passage not obtained in this check.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [R03_access_result.json](evidence/R03_access_result.json)
### R04|[Ogitani et al. — Bystander killing effect of DS-8201a in tumors with HER2 heterogeneity](https://onlinelibrary.wiley.com/doi/full/10.1111/cas.12966)
Publication / data / access: 2016-05-11 / Cell and mouse experiments reported in 2016 / 2026-10-07
Neighboring-cell effects of a membrane-permeable payload; normal-tissue safety cannot be inferred.
Abstract and methods/results content on the public research page.
R1 access scope retained; not reread in this round
### R05|[Lyon et al. — Reducing hydrophobicity of homogeneous antibody-drug conjugates improves pharmacokinetics and therapeutic index](https://pubmed.ncbi.nlm.nih.gov/26076429/)
Publication / data / access: 2015-06-15 / Preclinical research reported in 2015 / 2026-10-07
The named Lyon study example and citation have been removed from the text’s active evidence. This reference remains pending verification; the original research records are preserved.
The original URL failed in this round, and the old reference returned only an HHS shell. The original abstract was not retrieved, and no alternative route was used. Locator: No verifiable original-text locator; the retrieval record is in R05.txt.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [R05.txt](evidence/R05.txt)
### R06|[Yamazaki et al. — Antibody-drug conjugates with dual payloads for combating breast tumor heterogeneity and drug resistance](https://www.nature.com/articles/s41467-021-23793-7)
Publication / data / access: 2021-06-10 / Preclinical research reported in 2021 / 2026-10-07
Dual payloads may remain within one mechanism class; the resistance evidence is preclinical.
Abstract, design and results passages in the public Nature/PMC index; original figures were not reproduced.
R1 access scope retained; not reread in this round
### R07|[AstraZeneca/Daiichi Sankyo and Summit collaborate to evaluate Datroway plus ivonescimab](https://www.astrazeneca.com/media-centre/press-releases/2026/az-ds-collaboration-with-summit-for-datroway.html)
Publication / data / access: 2026-10-02 / 2026-10-02 / 2026-10-07
Drug supply, cost sharing and retained rights; phase 3 initiation remains a plan. For R2, the “Daiichi Sankyo collaboration” section was also checked: Enhertu / Datroway alliances began in 2019-03 / 2020-07; co-development and commercialization outside Japan, exclusive Daiichi Sankyo rights in Japan, and Daiichi Sankyo manufacturing and supply.
Public full text
Original reread for the R2 company diagram
### R08|[AstraZeneca completes USD 2 billion equity investment in Summit Therapeutics](https://www.astrazeneca.com/media-centre/press-releases/2026/astrazeneca-completes-equity-investment-in-summit-therapeutics.html)
Publication / data / access: 2026-10-05 / 2026-10-05 / 2026-10-07
Supports AstraZeneca’s October 5, 2026 announcement that it completed a USD 2 billion equity investment in Summit, distinguished from clinical collaborations and a separate Datroway agreement.
Relevant paragraphs of the equity-completion announcement were read; the equity investment is not an ADC license fee and does not establish efficacy. Locator: Date and transaction at lines 182–188; equity completion at 184; separate collaborations and agreement at 185–186.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [R08.txt](evidence/R08.txt)
### R09|[Kaufman et al. — HDP-101: The Anti-BCMA Antibody-Drug Conjugate HDP-101 with a Novel Amanitin Payload Shows Promising Initial First in Human Results in Relapsed Multiple Myeloma (AACR 2024, CT067)](https://heidelberg-pharma.com/images/managed/HDP-101-01_AACR2024_final.pdf)
Publication / data / access: 2024 / AACR 2024 poster; only the mechanism passages are cited here / 2026-10-07
Supports only the mechanism of HDP-101’s synthetic amanitin payload inhibiting RNA polymerase II. The poster’s older clinical results do not represent its 2026 status.
The one-page poster text at the original URL was read; only the necessary Introduction/Background mechanism passages are used. Locator: Page 1: Introduction, lines 24–27; Background, 30–35; year/CT067, 44–46.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [R09.txt](evidence/R09.txt)
### R10|[Kang et al. — Engineering a HER2-specific antibody-drug conjugate to increase lysosomal delivery and therapeutic efficacy](https://pmc.ncbi.nlm.nih.gov/articles/PMC6668989/)
Publication / data / access: 2019-04-01 / Not stated / 2026-10-07
Engineered anti-HER2 antibody–antigen dissociation at endosomal pH and increased lysosomal accumulation in the studied ADCs; no verification of an intact ADC–antigen recycling branch or DCB/LYSward.
Public full text. Published online 2019-04-01; cell and mouse experiments. No human benefit is established.
New primary source checked for R2
### C01|[FDA: Approval of T-DXd + pertuzumab in first-line HER2+ metastatic breast cancer](https://www.fda.gov/drugs/drug-approvals-and-databases/fda-approves-fam-trastuzumab-deruxtecan-nxki-pertuzumab-unresectable-or-metastatic-her2-positive)
Publication / data / access: 2025-12-15 / 2025-12-15 / 2026-10-07
Breast09 approval and PFS difference; OS immature in the approval analysis.
The full public FDA approval announcement was reviewed; no approval or reimbursement status in other markets is inferred.
R1 access scope retained; not reread in this round
### C02|[FDA: Two approvals for neoadjuvant and adjuvant T-DXd in HER2+ early-stage breast cancer](https://www.fda.gov/drugs/resources-information-approved-drugs/fda-approves-two-separate-indications-fam-trastuzumab-deruxtecan-nxki-her2-positive-early-stage)
Publication / data / access: 2026-05-15 / 2026-05-15 / 2026-10-07
Breast11 pathological response and the direct comparison of three-year iDFS in Breast05.
The full public FDA approval announcement was reviewed; no approval or reimbursement status in other markets is inferred.
R1 access scope retained; not reread in this round
### C03|[FDA: Datroway approval in first-line TNBC for patients not candidates for PD-(L)1 therapy](https://www.fda.gov/drugs/resources-information-approved-drugs/fda-approves-datopotamab-deruxtecan-dlnk-unresectable-or-metastatic-triple-negative-breast-cancer)
Publication / data / access: 2026-05-22 / 2026-05-22 / 2026-10-07
PFS, OS and indication scope in TNBC patients not candidates for immunotherapy.
The full public FDA approval announcement was reviewed; no approval or reimbursement status in other markets is inferred.
R1 access scope retained; not reread in this round
### C04|[FDA: Datroway approval in HR+/HER2− breast cancer](https://www.fda.gov/drugs/resources-information-approved-drugs/fda-approves-datopotamab-deruxtecan-dlnk-unresectable-or-metastatic-hr-positive-her2-negative-breast)
Publication / data / access: 2025-01-17 / 2025-01-17 / 2026-10-07
PFS benefit in Breast01; this cannot be restated as a positive OS result.
The full public FDA approval announcement was reviewed; no approval or reimbursement status in other markets is inferred.
R1 access scope retained; not reread in this round
### C05|[FDA: Accelerated approval of Datroway in EGFR-mutated NSCLC](https://www.fda.gov/drugs/resources-information-approved-drugs/fda-grants-accelerated-approval-datopotamab-deruxtecan-dlnk-egfr-mutated-non-small-cell-lung-cancer)
Publication / data / access: 2025-06-23 / 2025-06-23 / 2026-10-07
ORR in the pooled subgroup of previously treated EGFR-mutated lung cancer; OS superiority not established.
The full public FDA approval announcement was reviewed; no approval or reimbursement status in other markets is inferred.
R1 access scope retained; not reread in this round
### C06|[FDA: First-line TNBC approvals for Trodelvy alone and with pembrolizumab](https://www.fda.gov/drugs/resources-information-approved-drugs/fda-approves-sacituzumab-govitecan-hziy-monotherapy-and-combination-pembrolizumab-first-line)
Publication / data / access: 2026-06-24 / 2026-06-24 / 2026-10-07
PFS and populations in ASCENT-03/04; OS remained immature.
The full public FDA approval announcement was reviewed; no approval or reimbursement status in other markets is inferred.
R1 access scope retained; not reread in this round
### C07|[FDA: Traditional approval of EV + pembrolizumab in advanced urothelial cancer](https://www.fda.gov/drugs/resources-information-approved-drugs/fda-approves-enfortumab-vedotin-ejfv-pembrolizumab-locally-advanced-or-metastatic-urothelial-cancer)
Publication / data / access: 2023-12-15 / 2023-12-15 / 2026-10-07
OS and PFS at EV-302 approval; these are not the 2026 follow-up values.
The full public FDA approval announcement was reviewed; no approval or reimbursement status in other markets is inferred.
R1 access scope retained; not reread in this round
### C08|[FDA: Perioperative EV + pembrolizumab approval in MIBC expanded to cisplatin-eligible patients](https://www.fda.gov/drugs/resources-information-approved-drugs/fda-approves-pembrolizumab-or-pembrolizumab-and-berahyaluronidase-alfa-pmph-each-enfortumab-vedotin)
Publication / data / access: 2026-07-10 / 2026-07-10 / 2026-10-07
EFS, OS and approved population in EV-304 versus a platinum-containing neoadjuvant strategy.
The full public FDA approval announcement was reviewed; no approval or reimbursement status in other markets is inferred.
R1 access scope retained; not reread in this round
### C09|[Shitara et al. Trastuzumab Deruxtecan or Ramucirumab plus Paclitaxel in Gastric Cancer](https://pubmed.ncbi.nlm.nih.gov/40454632/)
Publication / data / access: 2025-05-31 / Not stated / 2026-10-07
The Gastric04 numerical and repeat-biopsy example has been removed from the text. This source remains a historical reference awaiting verification, not active evidence for this version.
The original PubMed URL returned HTTP 429 in this round; neither the abstract nor full text was retrieved. No alternative route was used. Locator: No verifiable original-text locator; the retrieval record is in C09.txt.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C09.txt](evidence/C09.txt)
### C10|[Yang et al. Izalontamab brengitecan versus chemotherapy in recurrent/metastatic NPC](https://pubmed.ncbi.nlm.nih.gov/41125110/)
Publication / data / access: 2025-10-19 / Not stated / 2026-10-07
Supports the population, chemotherapy comparator, ORR and grade ≥3 treatment-related adverse events in the phase 3 NPC trial in China; it does not substantiate the adjacent TNBC results.
PubMed abstract and bibliographic information were retrieved; the journal full text was not read. The abstract does not state an exact data cutoff. Locator: PMID 41125110, Abstract: Methods and Findings; retrieved-text lines 296–300.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C10.txt](evidence/C10.txt)
### C11|[BMS/SystImmune: Interim phase 3 OS/PFS results for iza-bren in TNBC and ESCC](https://news.bms.com/news/details/2026/Izalontamab-Brengitecan-Iza-Bren-Demonstrates-Statistically-Significant-and-Clinically-Meaningful-Improvements-in-Overall-Survival-and-Progression-Free-Survival-in-Patients-with-Triple-Negative-Breast-Cancer-and-Esophageal-Squamous-Cell-Carcinoma/default.aspx)
Publication / data / access: 2026-06-02 / Not stated / 2026-10-07
Supports the interim OS figures and population for PANKU-Breast02 in China and the company-reported evidence level for the TNBC/ESCC phase 3 results. BMS/SystImmune joint development applies outside China.
The relevant trial, mechanism and collaboration sections of the company announcement were read; this is not a journal full text or independent confirmation of efficacy. Locator: PANKU-Breast02 section, lines 25–33; territorial responsibilities, line 44; About iza-bren, lines 46–48.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C11.txt](evidence/C11.txt)
### C12|[Raab et al. HDP-101 IMS 2026 poster PA-216](https://heidelberg-pharma.com/images/managed/HDP-101-01_IMS_poster.pdf)
Publication / data / access: 2026-09-24 / 2026-09-03 / 2026-10-07
Supports 53 patients dosed in phase 1, the 175 µg/kg RP2D, the start of phase 2a expansion, and split-first-dose/premedication measures for HDP-101.
The previously used reference returned the one-page poster text at the same original URL. Only the necessary sections were checked; the poster image was not rechecked. Locator: Page 1: Study Progress, lines 43–53; Results, 57–62; PK/PD, 83–86; data cutoff, 128.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C12.txt](evidence/C12.txt)
### C13|[Daiichi Sankyo/MSD: Ifinatamab deruxtecan BLA voluntarily withdrawn](https://www.daiichisankyo.com/files/news/pressrelease/pdf/202609/20260925_E.pdf)
Publication / data / access: 2026-09-25 / 2026-09-25 / 2026-10-07
Withdrawal and continued phase 3 development; the former PDUFA date no longer applied, and detailed causation was not disclosed.
The full public company regulatory status announcement was reviewed; internal FDA review comments were not obtained.
R1 access scope retained; not reread in this round
### C14|[Daiichi Sankyo: IDeate-Lung01 primary results at WCLC2025](https://daiichisankyo.us/press-releases/-/article/ifinatamab-deruxtecan-demonstrated-clinically-meaningful-response-rates-in-patients-with-extensive-stage-small-cell-lung-cancer-in-ideate-lung01-phase-2-trial)
Publication / data / access: 2025-09-07 / 2025-03-03 / 2026-10-07
ORR, DOR and ILD in the 137-patient dose cohort; no standard-of-care comparator.
The full company announcement of original trial results was reviewed. The JCO paper was not successfully obtained in this review; no claim is made to have read its full text.
R1 access scope retained; not reread in this round
### C15|[Tolaney et al. Trastuzumab Deruxtecan plus Pertuzumab for HER2-Positive Metastatic Breast Cancer](https://pubmed.ncbi.nlm.nih.gov/41160818/)
Publication / data / access: 2025-10-29 / 2025-02-26 / 2026-10-07
PFS and safety for two arms, with the third still blinded; OS was immature.
The public abstract of the original paper was reviewed; the journal’s paywalled full text was not obtained.
R1 access scope retained; not reread in this round
### C16|[AstraZeneca H1 and Q2 2026 Clinical Trials Appendix](https://www.astrazeneca.com/content/dam/az/PDF/2026/h1q2/H1-and-Q2-2026-results-clinical-trials-appendix.pdf)
Publication / data / access: 2026-07-27 / 2026-07-27 / 2026-10-07
Supports this 2026-07-27 edition’s anticipated-data windows: H2 2026 for AVANZAR/Lung15, H1 2027 for Lung07/08, and H2 2027 for Breast03. This edition cannot establish the earlier H2 2026 expectation or a historical timing change.
Only the necessary ADC trial rows and dates in the 154-page public PDF were checked; the complete document was not analyzed. Locator: Printed page 15: Breast03; page 16: the Status column for AVANZAR, Lung07, Lung08 and Lung15.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C16.txt](evidence/C16.txt)
### C17|[ClinicalTrials.gov: A Study Comparing BL-B01D1 With Chemotherapy of Physician's Choice in Patients With Unresectable Locally Advanced or Metastatic Triple-Negative Breast Cancer(PANKU-Breast02)](https://clinicaltrials.gov/study/NCT06382142)
Publication / data / access: 2024-04-24 / 2026-07-23 / 2026-10-07
Supports PANKU-Breast02’s exclusion of prior ADCs with a TOPI-inhibitor payload; it is not a source of trial outcomes.
Previously saved official API field extracts were reviewed; the registry was not refreshed online. The complete original HTTP JSON was not saved. Locator: NCT06382142: saved first eligibility exclusion and last-update field.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C17.txt](evidence/C17.txt)
### C18|[ClinicalTrials.gov: A Study of Dato-DXd Versus Investigator's Choice Chemotherapy in Patients With Locally Recurrent Inoperable or Metastatic Triple-negative Breast Cancer, Who Are Not Candidates for PD-1/PD-L1 Inhibitor Therapy (TROPION-Breast02)](https://clinicaltrials.gov/study/NCT05374512)
Publication / data / access: 2022-05-16 / 2026-05-15 / 2026-10-07
First-line Dato population and exclusion of prior TOP1 treatment.
The registry record was read directly through the official ClinicalTrials.gov public API; it is not a results paper.
R1 access scope retained; not reread in this round
### C19|[ClinicalTrials.gov: Study of Sacituzumab Govitecan-hziy Versus Treatment of Physician's Choice in Patients With Previously Untreated Locally Advanced Inoperable or Metastatic Triple-Negative Breast Cancer](https://clinicaltrials.gov/study/NCT05382299)
Publication / data / access: 2022-05-19 / 2026-04-06 / 2026-10-07
First-line SG population and exclusion of prior TOP1 treatment.
The registry record was read directly through the official ClinicalTrials.gov public API; it is not a results paper.
R1 access scope retained; not reread in this round
### C20|[ClinicalTrials.gov: Study of Sacituzumab Govitecan-hziy and Pembrolizumab Versus Treatment of Physician's Choice and Pembrolizumab in Patients With Previously Untreated, Locally Advanced Inoperable or Metastatic Triple-Negative Breast Cancer](https://clinicaltrials.gov/study/NCT05382286)
Publication / data / access: 2022-05-19 / 2025-09-18 / 2026-10-07
SG plus immunotherapy population and exclusion of prior TOP1 treatment.
The registry record was read directly through the official ClinicalTrials.gov public API; it is not a results paper.
R1 access scope retained; not reread in this round
### C21|[ClinicalTrials.gov: A Study of Trastuzumab Deruxtecan (T-DXd) Versus Trastuzumab Emtansine (T-DM1) in High-risk HER2-positive Participants With Residual Invasive Breast Cancer Following Neoadjuvant Therapy (DESTINY-Breast05)](https://clinicaltrials.gov/study/NCT04622319)
Publication / data / access: 2020-11-09 / 2026-05-15 / 2026-10-07
Supports DB05’s exclusion of prior T-DXd, T-DM1 or other HER2 ADCs and its postoperative comparison. C02 is the source for the adjacent DB11/DB05 outcome percentages.
Previously saved official API field extracts were reviewed without an online registry refresh; this is not a results paper. Locator: NCT04622319: saved prior_adc_or_specific_exclusions[1], official trial title and primary-outcome fields.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C21.txt](evidence/C21.txt)
### C22|[ClinicalTrials.gov: Trastuzumab Deruxtecan (T-DXd) With or Without Pertuzumab Versus Taxane, Trastuzumab and Pertuzumab in HER2-positive Metastatic Breast Cancer (DESTINY-Breast09)](https://clinicaltrials.gov/study/NCT04784715)
Publication / data / access: 2021-03-05 / 2026-07-30 / 2026-10-07
Supports DB09’s estimated primary completion on 2026-11-11, its 2026-07-30 update date and three-arm design; it does not establish a publication date.
Previously saved official API date and design fields were reviewed; no online registry refresh was performed. Locator: NCT04784715: status.primaryCompletionDateStruct, lastUpdatePostDateStruct and the three-arm design field.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C22.txt](evidence/C22.txt)
### C23|[ClinicalTrials.gov: A Study of Ifinatamab Deruxtecan Versus Treatment of Physician's Choice in Subjects With Relapsed Small Cell Lung Cancer](https://clinicaltrials.gov/study/NCT06203210)
Publication / data / access: 2024-01-12 / 2026-08-06 / 2026-10-07
Supports IDeate-Lung02’s estimated primary completion on 2028-01-30, outside the report’s twelve-month window. C13 is responsible for the withdrawal and PDUFA statements.
Previously saved official API date fields were reviewed; no online registry refresh was performed. Locator: NCT06203210: status.primaryCompletionDateStruct and lastUpdatePostDateStruct.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C23.txt](evidence/C23.txt)
### C24|[ClinicalTrials.gov: A Study of Dato-DXd With or Without Durvalumab Versus Investigator's Choice of Therapy in Patients With Stage I-III Triple-negative Breast Cancer Without Pathological Complete Response Following Neoadjuvant Therapy (TROPION-Breast03)](https://clinicaltrials.gov/study/NCT05629585)
Publication / data / access: 2022-11-29 / 2026-06-15 / 2026-10-07
Supports Breast03’s estimated primary completion on 2027-09-20 and its residual-disease TNBC/iDFS design after neoadjuvant treatment. The H2 2027 company guidance comes from C16.
Previously saved official API date and study-design fields were reviewed; no online registry refresh was performed. Locator: NCT05629585: status.primaryCompletionDateStruct, official_title and primary_outcomes[0].
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [C24.txt](evidence/C24.txt)
### D01|[Daiichi Sankyo and Merck Announce Global Development and Commercialization Collaboration for Three Daiichi Sankyo DXd ADCs](https://www.merck.com/news/daiichi-sankyo-and-merck-announce-global-development-and-commercialization-collaboration-for-three-daiichi-sankyo-dxd-adcs/)
Publication / data / access: 2023-10-19 / 2023-10-19 / 2026-10-07
USD 4 billion upfront, conditional continuation payments and milestones; manufacturing is Daiichi Sankyo’s responsibility.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
Original reread for the R2 company diagram
### D02|[Merck Q2 2026 Form 10-Q, collaboration footnote](https://www.sec.gov/Archives/edgar/data/310158/000031015826000212/R10.htm)
Publication / data / access: 2026-08-07 / 2026-06-30 / 2026-10-07
Verifies payment of USD 4 billion and two USD 750 million installments; separately records the subsequent cost-sharing amendment.
The transaction or collaboration notes used from the public SEC filing were read. This does not claim page-by-page analysis of the entire financial report.
R1 access scope retained; not reread in this round
### D03|[Ifinatamab Deruxtecan BLA Voluntarily Withdrawn](https://www.merck.com/news/ifinatamab-deruxtecan-biologics-license-application-for-certain-patients-with-previously-treated-extensive-stage-small-cell-lung-cancer-voluntarily-withdrawn/)
Publication / data / access: 2026-09-25 / 2026-09-25 / 2026-10-07
Withdrawal from the accelerated-approval pathway and continued Phase 3 development; not termination of development.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D04|[Patritumab Deruxtecan BLA Receives Complete Response Letter Due to Third-Party Manufacturer Inspection](https://www.merck.com/news/patritumab-deruxtecan-bla-submission-receives-complete-response-letter-from-fda-due-to-inspection-findings-at-third-party-manufacturer/)
Publication / data / access: 2024-06-26 / 2024-06-26 / 2026-10-07
Supports the companies’ account of the 2024 patritumab deruxtecan CRL: third-party manufacturer inspection findings, with no efficacy or safety data issues identified in that announcement.
Relevant opening paragraphs of the company announcement were read; the FDA CRL itself was not obtained. Locator: Opening announcement paragraphs, lines 94–110, especially 104–105.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D04.txt](evidence/D04.txt)
### D05|[Patritumab Deruxtecan BLA Voluntarily Withdrawn](https://www.merck.com/news/patritumab-deruxtecan-biologics-license-application-for-patients-with-previously-treated-locally-advanced-or-metastatic-egfr-mutated-non-small-cell-lung-cancer-voluntarily-withdrawn/)
Publication / data / access: 2025-05-29 / 2025-05-29 / 2026-10-07
Supports the 2025 voluntary BLA withdrawal and the stated reason involving non-significant OS in the confirmatory trial; the release explicitly separates it from the 2024 manufacturing inspection issue.
The withdrawal rationale and joint-development paragraphs were read; this release does not verify the original collaboration’s payments or amendments. Locator: Opening paragraphs, lines 94–105, especially 96–98.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D05.txt](evidence/D05.txt)
### D06|[Daiichi Sankyo Announces Losses Related to Review of Product Supply Plans and Revision of FY2025 Forecast](https://www.daiichisankyo.com/files/news/pressrelease/pdf/202605/20260508_E.pdf)
Publication / data / access: 2026-05-08 / 2026-03-31 / 2026-10-07
Lower demand assumptions, minimum purchase obligations and two distinct charges; not evidence of cash already paid.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D07|[Pfizer Completes Acquisition of Seagen](https://www.pfizer.com/news/press-release/press-release-detail/pfizer-completes-acquisition-seagen)
Publication / data / access: 2023-12-14 / 2023-12-14 / 2026-10-07
Supports Pfizer’s December 2023 completion of the acquisition of all outstanding Seagen common stock and incorporation of its ADC and other oncology assets.
The company’s acquisition-completion release was read; exchange delisting documentation was not separately checked. Locator: Acquisition-completion section, lines 101–112; all outstanding common stock at line 107.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D07.txt](evidence/D07.txt)
### D08|[Pfizer Q2 2024 acquisition note, Seagen purchase accounting](https://www.sec.gov/Archives/edgar/data/78003/000007800324000166/R10.htm)
Publication / data / access: Not stated / 2024-06-30 / 2026-10-07
Consideration transferred and the amount net of acquired cash, on a different basis from announced enterprise value.
The transaction or collaboration notes used from the public SEC filing were read. This does not claim page-by-page analysis of the entire financial report.
R1 access scope retained; not reread in this round
### D09|[AbbVie to Acquire ImmunoGen, including ELAHERE](https://investors.abbvie.com/news-releases/news-release-details/abbvie-acquire-immunogen-including-its-flagship-cancer-therapy)
Publication / data / access: 2023-11-30 / 2023-11-30 / 2026-10-07
Announced equity value and cash consideration per share; not the final accounting amount.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D10|[AbbVie Completes Acquisition of ImmunoGen](https://news.abbvie.com/2024-02-12-AbbVie-Completes-Acquisition-of-ImmunoGen)
Publication / data / access: 2024-02-12 / 2024-02-12 / 2026-10-07
Supports AbbVie’s February 2024 completion of the ImmunoGen acquisition, including ELAHERE and the ADC pipeline.
The title, date, acquisition and portfolio paragraphs were read; historical product descriptions were not used to update subsequent regulatory status. Locator: Date at line 9; portfolio and completion paragraphs at lines 15–27, especially 15–16, 20 and 25.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D10.txt](evidence/D10.txt)
### D11|[AbbVie 2024 Form 10-K acquisition footnote, finalized ImmunoGen valuation](https://www.sec.gov/Archives/edgar/data/1551152/000155115225000020/R14.htm)
Publication / data / access: Not stated / 2024-12-31 / 2026-10-07
Final shareholder consideration and amount net of acquired cash; employee award expense is presented separately.
The transaction or collaboration notes used from the public SEC filing were read. This does not claim page-by-page analysis of the entire financial report.
R1 access scope retained; not reread in this round
### D12|[BioNTech and DualityBio Form Global Strategic Partnership](https://www.biontech.com/int/en/home/mediaroom/news/press-releases/2023/04/biontech-and-dualitybio-form-global-strategic-partnership.html)
Publication / data / access: 2023-04-03 / 2023-04-03 / 2026-10-07
Supports the territories and responsibilities in the 2023 BioNTech–DualityBio two-ADC collaboration and establishment of the US DB-1311 cost/profit-and-loss-sharing option.
The original collaboration terms were read; this 2023 release does not establish exercise of the option in 2026, which is supported by D13. Locator: Collaboration and rights terms, lines 36–51, especially 39–40 and 49–51.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D12.txt](evidence/D12.txt)
### D13|[DualityBio Announces 2026 Interim Results and Corporate Updates](https://en.dualitybiologics.com/news/615.html)
Publication / data / access: 2026-08-28 / 2026-06-30 / 2026-10-07
Supports the company’s statement that it notified BioNTech in May 2026 of exercise of the US DB-1311/BNT324/elfe-D cost-and-profit/loss-sharing option, and supports the relevant asset aliases.
The partnership and related financial sections of the 2026 interim release were read; these company disclosures do not establish clinical superiority of the platform. Locator: Date and reporting period at lines 30 and 43; aliases at 36–43; option exercise at 148–155, especially 154.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D13.txt](evidence/D13.txt)
### D14|[Gilead and Tubulis Enter Exclusive Option and License Agreement](https://investors.gilead.com/news/news-details/2024/Gilead-and-Tubulis-Enter-Into-Exclusive-Option-and-License-Agreement-to-Develop-ADC-Candidate-for-Select-Solid-Tumor-Target/default.aspx)
Publication / data / access: 2024-12-03 / 2024-12-03 / 2026-10-07
Supports the Gilead–Tubulis single-asset option agreement: USD 20 million upfront, a conditional USD 30 million option fee and up to USD 415 million in milestones, totaling up to USD 465 million, with sales royalties additional.
The original option and license terms were read; USD 465 million is the sum of the specified fees and milestones, not receipts, and subsequent exercise was not verified here. Locator: Single-asset scope and responsibilities at lines 31–40; financial terms and royalties at line 39.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D14.txt](evidence/D14.txt)
### D15|[Gilead to Acquire Tubulis](https://www.gilead.com/news/news-details/2026/gilead-to-acquire-tubulis-adding-potentially-best-in-class-antibody-drug-conjugate-and-next-generation-platform-to-further-strengthen-oncology-pipeline)
Publication / data / access: 2026-04-07 / 2026-04-07 / 2026-10-07
Supports the agreed terms for Gilead’s acquisition of Tubulis: USD 3.15 billion upfront payable at closing, on the stated basis and subject to adjustments, plus up to USD 1.85 billion in milestones.
The agreement, planned integration and terms were read; the supplied publication date of 2026-04-07 is retained without a separately retrieved date header, and the closing scope of D16 and accounting scope of D17 are not imported. Locator: Agreement at line 304; integration at 311; terms at 314; conference-call date wording at 319.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D15.txt](evidence/D15.txt)
### D16|[Gilead Sciences Completes Acquisition of Tubulis](https://investors.gilead.com/news/news-details/2026/Gilead-Sciences-Completes-Acquisition-of-Tubulis-Further-Strengthening-Oncology-Portfolio/default.aspx)
Publication / data / access: 2026-05-21 / 2026-05-21 / 2026-10-07
Closing, organizational integration and candidate targets; platform advantages still require clinical validation.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
Original reread for the R2 company diagram
### D17|[Gilead Q2 2026 Form 10-Q, Tubulis acquisition](https://www.sec.gov/Archives/edgar/data/882095/000088209526000031/gild-20260630.htm)
Publication / data / access: 2026-08-06 / 2026-06-30 / 2026-10-07
Approximately USD 3.2 billion net of acquired cash and the asset-acquisition assessment; not solely a platform price.
The transaction or collaboration notes used from the public SEC filing were read. This does not claim page-by-page analysis of the entire financial report.
R1 access scope retained; not reread in this round
### D18|[DualityBio Enters Global Collaboration and License with Genentech for DUPAC](https://en.dualitybiologics.com/news/614.html)
Publication / data / access: 2026-08-28 / 2026-08-28 / 2026-10-07
Supports the DualityBio–Genentech DUPAC collaboration and the development handoff after Phase 1a, with USD 45 million upfront, over USD 1 billion in conditional milestones and additional royalties.
The collaboration terms and DUPAC description were read; preclinical design claims do not establish human benefit, and receipt of the stated payments was not verified. Locator: Collaboration and financial terms at lines 28–38; responsibilities at 36; platform description at 46–48.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D18.txt](evidence/D18.txt)
### D19|[Tubulis Strategic License Agreement with Bristol Myers Squibb](https://tubulis.com/news/tubulis-announces-strategic-license-agreement-with-bristol-myers-squibb-to-develop-next-generation-adcs-for-the-treatment-of-cancer-patients-2/)
Publication / data / access: 2023-04-20 / 2023-04-20 / 2026-10-07
Division of antibody and payload responsibilities and signing terms; no precise milestone ceiling disclosed.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D20|[GSK and Hengrui agreements to develop up to 12 innovative medicines](https://www.gsk.com/en-gb/media/press-releases/gsk-and-hengrui-pharma-enter-agreements/)
Publication / data / access: 2025-07-28 / 2025-07-28 / 2026-10-07
A cross-therapeutic-area option package with no ADC-specific amount; excluded from aggregation.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D21|[Lonza Expands HPAPI Capacity in Visp, Supporting Payload-Linker Manufacturing](https://www.lonza.com/news/2026-06-30-07-00)
Publication / data / access: 2026-06-30 / 2026-06-30 / 2026-10-07
Supports Lonza’s plan to expand HPAPI and payload-linker capabilities in Visp, with operations expected in 2028.
The expansion scope and schedule were read; this is a company plan for future capacity, not evidence of current operation or customer orders. Locator: Expansion release, lines 16–26; facilities and integrated capabilities at 24–25, expected operations at 26.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D21.txt](evidence/D21.txt)
### D22|[Lonza Strengthens Advanced Synthesis Capabilities](https://www.lonza.com/media-advisories/2026-02-19-09-00)
Publication / data / access: 2026-02-19 / 2026-02-19 / 2026-10-07
Supports Lonza’s integration of the Synaffix platform and the role of Oss in prototyping, toxicology materials, and process/analytical development.
The Advanced Synthesis capabilities and Oss responsibilities were read; descriptions of capabilities do not establish human advantages for each candidate or commercial orders. Locator: Capabilities advisory, lines 16–27; platform at 19 and 22–24; Oss role at 27.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D22.txt](evidence/D22.txt)
### D23|[WuXi XDC Celebrates GMP Release of Singapore Site](https://wuxixdc.com/wuxi-xdc-celebrates-gmp-release-of-singapore-site-ushering-in-a-new-era-of-global-expansion/)
Publication / data / access: 2026-09-22 / 2026-09-21 / 2026-10-07
Supports the August 2026 GMP release of WuXi XDC’s Singapore BCM3 and DP4 facilities and the expected end-2026 timing for BCM4.
The company’s facility announcement was read; September 22 is the page date and September 21 the ceremony date, while GMP release does not establish individual product approval or customer orders. Locator: Dates and events at lines 111–117; facility releases and BCM4 timing at 161–164.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D23.txt](evidence/D23.txt)
### D24|[AstraZeneca breaks ground on Singapore ADC facility](https://www.astrazeneca.com/country-sites/singapore/press-releases/astrazeneca-to-hire-over-800-employees-to-produce-cancer-medicines-at-adc-manufacturing-facility-in-singapore.html)
Publication / data / access: 2024-11-07 / 2024-11-07 / 2026-10-07
Supports the planned end-to-end scope of AstraZeneca’s USD 1.5 billion Singapore ADC facility and expected operations in 2029.
The investment and process sections of the 2024 groundbreaking release were read; this is a future construction plan, and historical ticker boilerplate was not used to update listing status. Locator: Date at line 182; amount and timing at 195; antibody, drug/linker, conjugation and filling scope at 200.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D24.txt](evidence/D24.txt)
### D25|[Johnson & Johnson Completes Acquisition of Ambrx](https://www.investor.jnj.com/investor-news/news-details/2024/Johnson--Johnson-Completes-Acquisition-of-Ambrx/default.aspx)
Publication / data / access: 2024-03-07 / 2024-03-07 / 2026-10-07
Closing, ADC engineering and ARX517; Ambrx is not assigned an independent ticker.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D26|[BioNTech Q2 2026 financial results, SEC exhibit](https://www.sec.gov/Archives/edgar/data/1776985/000177698526000054/a991bntx_q22026pressreleas.htm)
Publication / data / access: 2026-08-04 / 2026-06-30 / 2026-10-07
Supports BioNTech’s BNT323/DB-1303 and BNT324/DB-1311 aliases and its event-accrual-based expectation for the DYNASTY-Breast02 primary analysis in Q4 2026.
The ADC pipeline section of the SEC-filed earnings release was read; an expected analysis is not a reported result, and this section does not verify exercise of US profit/loss sharing. Locator: Date and reporting period at line 24; ADC section at 264–279, aliases at 265 and 278, expected analysis at 276.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D26.txt](evidence/D26.txt)
### D27|[Astellas: PADCEV plus Keytruda CHMP positive opinion for resectable MIBC](https://newsroom.astellas.com/2026-09-18-padcev-in-combination-with-keytruda-receives-positive-chmp-opinion-for-the-treatment-of-adults-with-resectable-mibc)
Publication / data / access: 2026-09-18 / 2026-09-18 / 2026-10-07
Supports the September 2026 positive CHMP opinion for PADCEV plus KEYTRUDA in resectable MIBC, distinguishing the cisplatin-eligible population from the existing EU indication.
The regulatory, population and collaboration paragraphs of Astellas’s release were read; a CHMP opinion is not a final European Commission approval and does not replace the original FDA source. Locator: Date and regulatory status at lines 265–276; populations at 267 and 275; collaboration relationships at 291–292.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [D27.txt](evidence/D27.txt)
### D28|[AstraZeneca investor FAQs: current stock exchanges](https://www.astrazeneca.com/investor-relations/faqs.html)
Publication / data / access: Not stated / Not stated / 2026-10-07
Verifies AZ listings in London, Stockholm and New York; the US exchange is not Nasdaq.
The public company investor page was read to verify current exchange listings and tickers.
R1 access scope retained; not reread in this round
### D29|[Roche conversion of Genussscheine ROG to participation certificates ROP](https://www.roche.com/investors/updates/inv-update-2026-03-16)
Publication / data / access: 2026-03-16 / 2026-03-17 / 2026-10-07
Effective date of the conversion from ROG to ROP; RO is a different security and is not interchangeable.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D30|[Lonza current investor relations](https://www.lonza.com/investor-relations)
Publication / data / access: Not stated / Not stated / 2026-10-07
Verifies Lonza’s SIX listing and LONN ticker; does not support efficacy for any individual product.
The public company investor page was read to verify current exchange listings and tickers.
R1 access scope retained; not reread in this round
### D31|[Pfizer September 2026 investor call announcement (listing verification)](https://www.pfizer.com/news/press-release/press-release-detail/pfizer-invites-public-view-and-listen-webcast-november-3)
Publication / data / access: 2026-09-22 / 2026-09-22 / 2026-10-07
Verifies Pfizer’s current NYSE listing and PFE ticker; used solely to identify the company.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D32|[AbbVie September 2026 conference announcement (listing verification)](https://investors.abbvie.com/news-releases/news-release-details/abbvie-present-morgan-stanley-24th-annual-global-healthcare)
Publication / data / access: 2026-09-03 / 2026-09-03 / 2026-10-07
Verifies AbbVie’s current NYSE listing and ABBV ticker; used solely to identify the company.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D33|[Bristol Myers Squibb Q3 2026 reporting notice (listing verification)](https://news.bms.com/news/details/2026/Bristol-Myers-Squibb-to-Report-Results-for-Third-Quarter-2026-on-October-29-2026/default.aspx)
Publication / data / access: 2026-09-18 / 2026-09-18 / 2026-10-07
Verifies BMS’s current NYSE listing and BMY ticker; used solely to identify the company.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D34|[Johnson & Johnson reports Q2 2026 results (listing verification)](https://www.jnj.com/media-center/press-releases/johnson-johnson-reports-q2-2026-results-raises-2026-outlook)
Publication / data / access: 2026-07-15 / 2026-07-15 / 2026-10-07
Verifies Johnson & Johnson’s current NYSE listing and JNJ ticker; used solely to identify the company.
The full public company announcement was read. Company disclosures are distinguished from the author’s inferences.
R1 access scope retained; not reread in this round
### D35|[Gilead Sciences, Inc. 2025 Form 10-K — Trodelvy product sales and revenue recognition](https://www.sec.gov/Archives/edgar/data/882095/000088209526000006/gild-20251231.htm)
Publication / data / access: 2026-02-24 / 2025-12-31 / 2026-10-07
Same-table 2023/2024/2025 Trodelvy total product sales: USD 1,063 / 1,315 / 1,397 million; net-sales basis and management’s qualitative 2025 attribution.
Public original 10-K and filing index. Note 2 p65; Note 1 pp58–59; MD&A p40. Filed 2026-02-24, fiscal year ended 2025-12-31.
New primary source checked for R2
### T01|[OBI Pharma — Pipeline](https://www.obipharma.com/what-we-do/pipeline-overview/)
Publication / data / access: Not stated / Not stated / 2026-10-07
The company pipeline distinguishes OBI-902’s TROP2/GlycOBI glycan-site design from OBI-992’s cysteine conjugation and describes their human studies.
Relevant public pipeline passages were read. The page is undated; engineering features do not establish comparative benefit in humans. Locator: OBI-992 and OBI-902 sections; retrieved-text lines 133, 137 and 163–168.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T01.txt](evidence/T01.txt)
### T02|[ClinicalTrials.gov — NCT06480240 / OBI-992](https://clinicaltrials.gov/study/NCT06480240)
Publication / data / access: 2024-06-28 / 2025-08-08 / 2026-10-07
The OBI-992 registry lists Phase 1/2, active but not recruiting, estimated enrollment of 117, and no posted results.
The official public API was read directly and its response JSON retained. Completion dates are estimates, not confirmed readout dates. Locator: API fields protocolSection.statusModule, protocolSection.designModule and hasResults.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T02.txt](evidence/T02.txt) · [T02.api.json](evidence/T02.api.json)
### T03|[ClinicalTrials.gov — NCT07124117 / OBI-902](https://clinicaltrials.gov/study/NCT07124117)
Publication / data / access: 2025-08-15 / 2026-01-05 / 2026-10-07
The OBI-902 registry supports entry into human studies and recruiting status, with Phase 1/2 and estimated enrollment of 147.
The official public API was read directly and its response JSON retained. No results are posted; the registry alone does not establish engineering advantages. Locator: API fields protocolSection.statusModule, protocolSection.designModule and hasResults.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T03.txt](evidence/T03.txt) · [T03.api.json](evidence/T03.api.json)
### T04|[OBI Pharma and TegMine Therapeutics Sign Exclusive Global License Agreement for Glycan-Targeting ADC](https://www.accessnewswire.com/newsroom/en/healthcare-and-pharmaceutical/obi-pharma-and-tegmine-therapeutics-sign-exclusive-global-license-agr-1126261)
Publication / data / access: 2026-01-12 / 2026-01-12 / 2026-10-07
The company’s 2026-01-12 release supports TegMine’s glycan-targeting antibody, OBI’s conjugation/linker technologies and a global license; detailed financial terms are undisclosed.
Relevant company-issued ACCESS passages were read, without accessing the protected earlier announcement. This release neither establishes the December 2025 linkage nor confirms cash received. Locator: Release date, license terms and issuer; retrieved-text lines 12, 19–24 and 56.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T04.txt](evidence/T04.txt)
### T05|[GlycoNex Doses First Patient in Phase 1 Trial of GNX1021](https://glyconex.com.tw/news/2026/2026-08-03-gnx1021-first-patient-dosed)
Publication / data / access: 2026-08-03 / 2026-08-03 / 2026-10-07
The company identifies bLeB/Y as GNX1021’s glycan target and announced first-patient dosing in Japan in its Phase 1 study on 2026-08-03.
Relevant public announcement passages were read; the trial registry was not separately checked. The release does not identify GNX102 or its unconjugated-antibody status. Locator: Date, first-patient dosing, target and trial design; retrieved-text lines 14–23.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T05.txt](evidence/T05.txt)
### T06|[Formosa Pharmaceuticals Files Clinical Trial Application for TSY-110, an Antibody-Drug Conjugate Biosimilar Targeting HER2-Positive Breast Cancers](https://www.formosapharma.com/formosa-pharmaceuticals-files-clinical-trial-application-for-tsy-110-an-antibody-drug-conjugate-biosimilar-targeting-her2-positive-breast-cancers/)
Publication / data / access: 2026-08-28 / 2026-08-28 / 2026-10-07
The 2026-08-28 release reports a European CTA submission for TSY-110/EG12043, co-developed with EirGenix and referencing Kadcyla, with planned PK, safety and immunogenicity assessments.
Relevant company announcement passages were read. CTA submission and company-reported preclinical similarity do not establish authorization, dosing or biosimilar approval. Locator: CTA announcement and About TSY-110; retrieved-text lines 90–96.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T06.txt](evidence/T06.txt)
### T07|[Formosa Pharmaceuticals Announces Presentation of TSY-310 at the 2026 ASCO Annual Meeting](https://www.formosapharma.com/formosa-pharmaceuticals-announces-presentation-of-tsy-310-at-the-2026-asco-annual-meeting/)
Publication / data / access: 2026-05-22 / 2026-05-22 / 2026-10-07
The 2026-05-22 announcement presents TSY-310’s EGFR×ROR1 bispecific design and preclinical data.
Design and ASCO presentation details were read. They establish the announced evidence stage, without separately verifying the absence of human development through October 7. Locator: Opening announcement and Details/Highlights; retrieved-text lines 88 and 94–105.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T07.txt](evidence/T07.txt)
### T08|[Almac Discovery — Pipeline](https://www.almacgroup.com/discovery/pipeline)
Publication / data / access: Not stated / Not stated / 2026-10-07
Verification that TSY-310 was formerly ALM-401, its global license and its preclinical stage.
Almac's public pipeline page and the full licensing announcement dated 2025-05-06 were read. The pipeline page has no update date.
R1 access scope retained; not reread in this round
### T09|[EirGenix — ADC & Bioconjugates](https://www.eirgenix.com/antibody-drug-conjugate)
Publication / data / access: Not stated / Not stated / 2026-10-07
EirGenix names Formosa Laboratories as a strategic partner and describes integrated antibody, analytical, GMP-manufacturing and conjugation services.
Relevant public service passages were read. The undated page supports offered capabilities, not product-specific commercial orders or batch release. Locator: ADC & Bioconjugates and Monoclonal Antibody Development and Production; retrieved-text lines 87–95 and 109–125.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T09.txt](evidence/T09.txt)
### T10|[Formosa Laboratories — Antibody–Drug Conjugates](https://www.formosalab.com/tw/bioconjugation-adc)
Publication / data / access: Not stated / Not stated / 2026-10-07
Formosa Laboratories lists highly potent chemistry, conjugation, TFF/chromatographic purification, formulation and liquid filling/lyophilization; clinical-supply experience is company-reported.
Relevant public service passages were read. The page is undated; project counts and capacity aspirations were not used to infer current orders. Locator: One-stop solution and experience sections; retrieved-text lines 296–305 and 320.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T10.txt](evidence/T10.txt)
### T11|[Formosa Laboratories — Antibody–Drug Conjugate Facility](https://www.formosalab.com/tw/adc)
Publication / data / access: Not stated / Not stated / 2026-10-07
The company facility page lists 30–200 L conjugation reactors, ÄKTA, TFF and chromatography equipment.
Public facility specifications were read. The undated reactor volumes do not establish qualified annual product output or commercial sales. Locator: ADC manufacturing equipment list; retrieved-text lines 312–319.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T11.txt](evidence/T11.txt)
### T12|[Mycenax and RIN Sign License Agreement to Advance ADC Development Using RIN’s Proprietary Linker Technology](https://www.mycenax.com/news-detail.php?id=122&lang=en)
Publication / data / access: 2025-10-31 / 2025-10-31 / 2026-10-07
The 2025-10-31 release grants Mycenax rights to use RIN’s VLK linker in CDMO services worldwide and describes KriSan/Spera partnerships.
Public license and partnership passages were read. The rights were not expanded to all-use exclusivity, nor an antibody Phase 1 example treated as an ADC trial. Locator: Date, license paragraph and About RIN/Mycenax; retrieved-text lines 118, 124, 128, 141 and 149.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T12.txt](evidence/T12.txt)
### T13|[Mycenax — Antibody-Drug Conjugate](https://www.mycenax.com/cdmo.php?id=56)
Publication / data / access: Not stated / Not stated / 2026-10-07
Mycenax’s service page lists GMP-grade 50 L production and distinguishes anti-TMEM180 antibody Phase 1 supply from subsequent anti-IF ADC production.
ConjuMX, VLK and partnership passages were read. The undated 50 L figure is a company capability statement, not product-specific commercial release or orders. Locator: ConjuMX, VLK Linker and Strategic ADC Partners; retrieved-text lines 134–149 and 158–164.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T13.txt](evidence/T13.txt)
### T14|[Development Center for Biotechnology — LYSward: ADC Platform with pH-Regulated Antigen Binding](https://www.dcb.org.tw/technologies/67)
Publication / data / access: Not stated / 2026-04-09 / 2026-10-07
Historical R1 lead; not active R2 support for P01, the recycling branch or platform maturity.
The independent QA carried forward into this round received HTTP 403. Unverified; no bypass, login or private endpoint was used. The original source and R1 records are retained.
External QA reported HTTP 403; pending
### T15|[Taiwan Stock Exchange — Formosa Laboratories, Inc. Company Profile (4746)](https://www.twse.com.tw/pdf/ch/4746_ch.pdf)
Publication / data / access: Not stated / 2026-10-06 / 2026-10-07
The TWSE PDF read in this round supports Formosa Laboratories’ TWSE-listed status and ticker 4746.
The original 2026-10-06 PDF was not retained. The current same-URL file was generated on 2026-10-07, recorded separately from the unchanged original data date. Locator: PDF page 1: company name, listing date, ticker and generation date; extracted lines 35 and 42–48.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T15.txt](evidence/T15.txt)
### T16|[Taiwan Stock Exchange — EirGenix, Inc. Company Profile (6589)](https://www.twse.com.tw/pdf/ch/6589_ch.pdf)
Publication / data / access: Not stated / 2026-10-07 / 2026-10-07
The TWSE PDF supports EirGenix’s TWSE-listed status, ticker 6589 and listing date of 2025-07-21.
Page 1 text of the PDF generated on 2026-10-07 was read. Its date matches the original record, without asserting identical original-file bytes. Locator: PDF page 1: company name, listing date, ticker and generation date; extracted lines 35 and 40–46.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T16.txt](evidence/T16.txt)
### T17|[Taiwan Stock Exchange — Formosa Pharmaceuticals, Inc. Company Profile (6838)](https://www.twse.com.tw/pdf/ch/6838_ch.pdf)
Publication / data / access: Not stated / 2026-10-07 / 2026-10-07
The TWSE PDF supports Formosa Pharmaceuticals’ TWSE-listed status, ticker 6838 and listing date of 2024-08-13.
Page 1 text of the PDF generated on 2026-10-07 was read. Its date matches the original record, without asserting identical original-file bytes. Locator: PDF page 1: company name, listing date, ticker and generation date; extracted lines 35 and 40–46.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T17.txt](evidence/T17.txt)
### T18|[OBI Pharma — Corporate Overview](https://www.obipharma.com/investor-overview/corporate-overview/)
Publication / data / access: Not stated / Not stated / 2026-10-07
OBI’s corporate table lists 4174.TWO and Taipei Exchange, supporting TPEx-listed status and ticker 4174.
The public corporate table was read. It is undated and is used only for listing identity. Locator: Corporate Overview table; retrieved-text lines 126–132.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T18.txt](evidence/T18.txt)
### T19|[GlycoNex — Investor Relations](https://glyconex.com.tw/investors/)
Publication / data / access: Not stated / Not stated / 2026-10-07
GlycoNex’s investor page explicitly lists TPEx 4168 and Taipei Exchange-listed status.
Public identity and trading-market fields were read. The page is undated; its other financial figures were not adopted. Locator: Investor introduction, stock code and trading-market fields; retrieved-text lines 16–24.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T19.txt](evidence/T19.txt)
### T20|[Mycenax Biotech — Securities Information](https://www.mycenax.com/shareholders-meeting.php?id=5&lang=tw)
Publication / data / access: Not stated / Not stated / 2026-10-07
Mycenax’s securities page explicitly lists its common shares as Taipei Exchange-listed, with ticker 4726.
Public securities information was read. The page is undated and is used only for listing identity. Locator: Securities information; retrieved-text lines 125–127.
This evidence check covers only the listed claims and read level; see the source evidence index. [Evidence record](source_evidence.json) · [T20.txt](evidence/T20.txt)
### T21|[Drugnews — In-Depth Analysis on Vocus](https://drugnews.com.tw/subscribe.html)
Publication / data / access: Not stated / Not stated / 2026-10-07
An existing portal for continuing research; prices, promotions and promises of tool availability are not quoted.
The official public page was read. Capabilities are described within the source's scope; no internal or members-only material was obtained.
R1 access scope retained; not reread in this round
### T22|[Drugnews — Corporate Partnerships and Biomedical Content Advisory Services](https://drugnews.com.tw/services.html)
Publication / data / access: Not stated / Not stated / 2026-10-07
A portal for corporate research and advisory collaboration; no prices, exposure or outcomes are promised.
The official public page was read. Capabilities are described within the source's scope; no internal or members-only material was obtained.
R1 access scope retained; not reread in this round
---
[Changes and versions](changes.md) · [Figure sources](figure_sources.json) · [All sources CSV](sources.csv) · [Master records CSV](data/master_records.csv)